
Clinical Anatomy & Embryology
Exhaustive brachial and lumbosacral plexus nerve lesion locators, rotator cuff biomechanics, cranial nerve skull base foramina pathways, visual field defect decoders, comprehensive germ layer and organ embryology, thoracoabdominal cross-sections, and osteopathic structural correlates.
Authentic board questions covering plexus trauma, dermatomes, congenital anomalies, cranial neuropathies, and osteopathic structural correlates.
Upper Extremity & Brachial Plexus Injuries
Classic fracture sites, compression syndromes, motor deficits, and sensory loss patterns.
Radial Nerve
Runs in radial spiral groove of humerus with deep brachial (profunda brachii) artery.
Mechanism: Midshaft humerus fracture, compression in axilla ("Saturday night palsy" falling asleep with arm over chair, crutch palsy).
Motor Loss: Loss of elbow, wrist, and finger extension (BEST: Brachioradialis, Extensors of wrist/fingers, Supinator, Triceps).
Sensory Loss: Posterior arm and forearm; dorsal surface of hand (1st-3rd digits and webspace).
Median Nerve
Runs with brachial artery in cubital fossa, between FDS and FDP, passes through carpal tunnel.
Proximal Lesion (Supracondylar Fracture): Loss of wrist flexion, pronation, flexion of lateral digits. "Pope's blessing" (hand of benediction) when attempting to MAKE A FIST.
Distal Lesion (Carpal Tunnel / Lunate Dislocation): Thenar muscle atrophy (loss of thumb opposition → Ape Hand). Sensation lost over palmar aspects of thumb, index, middle, and radial half of ring finger.
Ulnar Nerve
Passes posterior to medial epicondyle ("funny bone") and through Guyon canal at wrist.
Mechanism: Medial epicondyle fracture (proximal) or hook of hamate fracture / cyclist handlebar neuropathy (distal Guyon canal).
Motor Loss: Hypothenar muscles, medial 2 lumbricals, all interossei (PAD/DAB: Palmar adduction, Dorsal abduction), adductor pollicis.
Clinical Signs: Froment Sign: Compensatory thumb IP flexion via FPL when gripping paper. Ulnar Paradox: Clawing is LESS severe with proximal lesions because FDP 4-5 are also paralyzed!
Axillary & Musculocutaneous
Erb-Duchenne vs Klumpke
Long Thoracic & Suprascapular
Hand Neurovascular Topography & Cutaneous Maps
Complete palmar and dorsal sensory territories, median nerve palmar cutaneous branch carpal tunnel sparing, recurrent thenar motor branch, and ulnar claw vs benediction sign.

Brachial Plexus Root-to-Terminal Topography
Complete root-to-terminal architecture, 3 cords relative to the axillary artery, Erb-Duchenne palsy (C5–C6), Klumpke claw hand (C8–T1), and winged scapula from long thoracic nerve injury.

Lower Extremity & Lumbosacral Plexus Injuries
Common peroneal foot drop, femoral nerve reflex loss, obturator adduction weakness, and Trendelenburg gait.
Common Peroneal (Fibular)
Wraps superficially around the neck of the fibula; most common lower extremity nerve injury.
Injury: Fibular head/neck fracture, tight lower leg plaster cast, or prolonged leg crossing.
Motor Deficit: Deep fibular branch → loss of ankle dorsiflexion (Foot Drop, high-stepping steppage gait). Superficial fibular → loss of eversion.
Sensory Deficit: Anterolateral lower leg and dorsum of foot (webbed space between 1st & 2nd toe = deep fibular).
Tibial Nerve
Courses through popliteal fossa and tarsal tunnel posterior to medial malleolus.
Injury: Knee trauma, Baker cyst in popliteal fossa, or compression under flexor retinaculum in tarsal tunnel.
Motor Deficit: Loss of foot plantarflexion (gastrocnemius, soleus), foot inversion (tibialis posterior), and toe flexion. Absent Achilles reflex (S1-S2).
Sensory Deficit: Loss of sensation on the sole (plantar surface) of the foot.
Femoral Nerve
Descends under inguinal ligament lateral to femoral artery within femoral triangle (outside femoral sheath!).
Injury: Pelvic fracture, psoas hematoma/abscess, or vascular access hematoma following femoral catheterization.
Motor Deficit: Loss of knee extension (quadriceps femoris) and weakened hip flexion (iliopsoas, pectineus, sartorius). Difficulty climbing stairs, frequent knee buckling.
Sensory & Reflex: Numbness of anterior thigh and medial leg (saphenous branch). Absent patellar tendon reflex (L3-L4).
From Lateral to Medial: Nerve → Artery → Vein → Empty space (femoral canal) → Lymphatics (deep node of Cloquet).
Crucial Board Fact: The Femoral Nerve is OUTSIDE the femoral sheath! The sheath encloses only the femoral artery, femoral vein, and femoral canal. Femoral hernias protrude into the femoral canal medial to the vein.
Obturator Nerve
Passes through obturator foramen to supply medial thigh compartment.
Injury: Pelvic ring fracture, anterior hip replacement surgery, or compression by an obturator hernia (Howship-Romberg sign).
Motor Deficit: Weakness of thigh adduction (adductor longus, brevis, and magnus; gracilis). Difficulty crossing legs while sitting.
Sensory Deficit: Small sensory patch over medial mid-thigh.
Superior Gluteal Nerve
Exits greater sciatic foramen superior to piriformis muscle.
Innervation: Gluteus medius, gluteus minimus, and tensor fasciae latae (hip abductors and pelvic stabilizers).
Mechanism: Intramuscular injections into superomedial quadrant of buttock or posterior hip dislocation.
Inferior Gluteal & Meralgia
Master Peripheral Nerve Traumatology Matrix
| Peripheral Nerve | Spinal Roots | High-Yield Anatomic Vulnerability | Motor Deficit / Presentation | Sensory Loss Distribution |
|---|---|---|---|---|
| Radial Nerve | C5–T1 | Midshaft humerus fracture, crutch pressure in axilla | Wrist drop, loss of finger and elbow extension (BEST muscles) | Posterior arm/forearm, dorsal webspace between thumb and index |
| Median Nerve | C5–T1 | Supracondylar fracture (proximal), carpal tunnel (distal) | Pope's blessing when making fist (proximal); Ape hand thenar atrophy (distal) | Palmar digits 1–3 and radial half of digit 4 (thenar palm spared in carpal tunnel) |
| Ulnar Nerve | C8–T1 | Medial epicondyle fracture, hook of hamate fracture / Guyon canal | Ulnar claw on finger extension, Froment sign (thumb IP flexion) | Medial 1.5 digits (little finger and ulnar half of ring finger) |
| Axillary Nerve | C5–C6 | Surgical neck humerus fracture, anterior glenohumeral dislocation | Impaired abduction >15° (deltoid) and external rotation (teres minor) | Sergeant's patch over lateral deltoid insertion |
| Common Peroneal (Fibular) | L4–S2 | Fibular head/neck fracture, tight plaster cast compression | Foot drop (loss of dorsiflexion), loss of foot eversion, steppage gait | Anterolateral leg, foot dorsum, 1st interdigital webspace (deep fibular) |
| Tibial Nerve | L4–S3 | Knee dislocation, Baker cyst in popliteal fossa, tarsal tunnel | Inability to stand on tiptoes (loss of plantarflexion), loss of inversion, lost ankle jerk | Sole (plantar surface) and heel of foot |
| Superior Gluteal Nerve | L4–S1 | Superomedial buttock injection, posterior hip surgery | Trendelenburg gait (contralateral pelvis drops when standing on affected leg) | None (purely motor nerve) |
| Femoral Nerve | L2–L4 | Psoas abscess/hematoma, femoral artery catheterization hematoma | Knee extension paralysis (quadriceps), knee buckling, lost patellar reflex | Anterior thigh, medial lower leg down to medial malleolus (saphenous) |
Lumbar Plexus Roots, Course & Clinical Entrapments
The lumbar plexus forms within the substance of the psoas major muscle from the ventral primary rami of L1–L4 (with contribution from T12). Recognition of each nerve's trajectory relative to the psoas border is essential for surgical navigation (inguinal hernia repairs, appendectomy, retroperitoneal dissection) and neurological localization.
| Nerve | Root | Psoas Relation & Trajectory | Motor Innervation | Sensory Field | High-Yield Board Entrapment / Injury |
|---|---|---|---|---|---|
| Subcostal | T12 | Runs inferior to 12th rib across quadratus lumborum | External/internal obliques, transversus abdominis, rectus | Skin over iliac crest and lower hypogastric region | Injured in flank incisions for nephrectomy or retroperitoneal lymphadenectomy. |
| Iliohypogastric | L1 | Lateral border of psoas, pierces transversus abdominis near ASIS | Internal oblique & transversus abdominis | Skin over lateral gluteal area and suprapubic / hypogastric zone | Injured during appendectomy (McBurney incision) or lower quadrant trocars → suprapubic numbness. |
| Ilioinguinal | L1 | Traverses superficial inguinal ring (does not enter deep ring!) | Internal oblique & transversus abdominis | Anterior scrotum / labia majora, root of penis, mons pubis | Most commonly injured nerve during open inguinal herniorrhaphy or Pfannenstiel incision → burning groin pain and scrotal numbness. |
| Genitofemoral | L1–L2 | Pierces anterior surface of psoas major, divides into 2 branches | Genital branch: Cremaster muscle (L1–L2 efferent limb) | Femoral branch: upper anterior thigh; Genital branch: scrotal/labial skin | Lost cremasteric reflex in testicular torsion, L1–L2 radiculopathy, or retroperitoneal hematoma. |
| Lateral Femoral Cutaneous | L2–L3 | Lateral border of psoas, passes under inguinal ligament medial to ASIS | None (purely sensory) | Skin of anterolateral thigh down to knee | Meralgia Paresthetica: Entrapped by tight belts, obesity, or pregnancy under inguinal ligament. Burning, stinging anterolateral thigh pain with normal motor exam. |
| Femoral | L2–L4 | Lateral border of psoas, under inguinal ligament lateral to femoral sheath | Iliopsoas, pectineus, sartorius, quadriceps femoris (knee extension) | Anterior thigh, medial lower leg & foot via saphenous nerve | Psoas abscess/hematoma, femoral artery catheterization complication → loss of knee extension, absent patellar reflex, knee buckling. |
| Obturator | L2–L4 | Medial border of psoas, descends through obturator foramen canal | Thigh adductors (adductor longus, brevis, magnus, gracilis) | Small cutaneous patch on distal medial thigh | Injured in pelvic lymphadenectomy (prostate/cervical cancer), obturator hernia (Howship-Romberg sign), or pelvic ring fracture → adduction failure. |
Nerve (Femoral nerve sits outside femoral sheath) • Artery (Femoral artery) • Vein (Femoral vein) • Lymphatics (Femoral canal / deep inguinal lymph nodes of Cloquet inside sheath). Femoral hernias protrude medial to the vein into the femoral canal.
Stroking the medial upper thigh stimulates the femoral branch of the genitofemoral nerve (and ilioinguinal nerve) as the afferent limb. Action potentials synapse in L1–L2 spinal cord, sending motor impulses via the genital branch of the genitofemoral nerve (efferent limb) to contract the cremaster muscle, retracting the ipsilateral testis.
Lower Extremity Nerves, Compartments & Gait Pathologies
Complete root origins, motor innervation, sensory distribution, and classic board presentations for Common Fibular (PED / foot drop), Tibial (TIP), Femoral, Obturator, and Superior Gluteal (Trendelenburg sign) nerves.

Phrenic vs. Vagus Mediastinal Courses & Recurrent Laryngeal Loops
Phrenic Nerve (C3, C4, C5)
Anterior to HilumCourse & Relations: Arises from C3–C5 ("C3, 4, 5 keeps the diaphragm alive"). Descends on the ANTERIOR surface of the Anterior Scalene muscle beneath the prevertebral fascia.
Thoracic Hilum Landmark: Passes ANTERIOR to the root (hilum) of the lung (sandwiched between parietal pericardium and mediastinal pleura with the pericardiacophrenic vessels).
Sensory Distribution: Transmits somatic sensory pain from central diaphragm, pericardium, and mediastinal pleura → referred pain to ipsilateral shoulder and neck tip (C3–C5 dermatome) via supraclavicular nerves.
Vagus Nerve (Cranial Nerve X)
Posterior to HilumCourse & Relations: Exits the jugular foramen, descends in the posterior groove of the Carotid Sheath between the internal jugular vein (lateral) and common/internal carotid artery (medial).
Thoracic Hilum Landmark: Passes POSTERIOR to the root (hilum) of the lung, breaking up into pulmonary and esophageal plexuses.
Diaphragmatic Hiatus: Reconstitutes as anterior (left vagus) and posterior (right vagus) vagal trunks: "LARP" (Left Anterior, Right Posterior) to traverse the esophageal hiatus at T10.
Recurrent Laryngeal Nerves
Asymmetric LoopsBranches of CN X providing motor supply to all intrinsic muscles of larynx EXCEPT cricothyroid (innervated by external branch of superior laryngeal nerve).
Left Recurrent Laryngeal: Loops under the Aortic Arch (lateral to ligamentum arteriosum) before ascending in the tracheoesophageal groove.
Right Recurrent Laryngeal: Loops under the Right Subclavian Artery at the root of the neck.
Upper & Lower Extremity Joints, Rotator Cuff & Ligaments
High-yield joint stabilizers, rotator cuff impingement tests, compartment borders, pediatric subluxations, and knee/ankle sports trauma.
Rotator Cuff (SITS) Master Functional Anatomy
Supraspinatus
Insertion: Superior facet of greater tubercle of humerus.
Action: Initiates arm abduction (first 0–15°) before deltoid (axillary nerve, 15–90°) and trapezius/serratus anterior (>90°).
Infraspinatus
Insertion: Middle facet of greater tubercle of humerus.
Action: External rotation of the humerus at the glenohumeral joint; dynamic posterior glenohumeral stabilization.
Teres Minor
Insertion: Inferior facet of greater tubercle of humerus.
Action: External rotation and adduction of humerus; forms superior border of triangular interval and inferior border of quadrangular space.
Subscapularis
Insertion: Lesser tubercle of humerus (only SITS muscle inserting on lesser tubercle!).
Action: Internal (medial) rotation and adduction of humerus; dynamic anterior glenohumeral stabilization.
Rotator Cuff (SITS) Kinematics & Posterior Scapular Spaces
Complete supraspinatus initiation (0–15°), external rotators (infraspinatus, teres minor), internal rotator (subscapularis on lesser tubercle), and neurovascular conduits: Quadrangular space (Axillary n., post. circumflex humeral a.), Triangular space (circumflex scapular a.), and Triangular interval (Radial n., profunda brachii a.).

Posterior Shoulder Anatomic Spaces
Vascular and neural conduits traversing between the axilla, scapular region, and posterior arm.
Quadrangular Space
Axillary N. + Post. Circumflex Humeral A.Borders: Superior: Teres minor (or subscapularis anteriorly); Inferior: Teres major; Medial: Long head of triceps; Lateral: Surgical neck of humerus.
Pathology: Quadrangular space syndrome (fibrous band compression) causes deltoid/teres minor weakness and lateral shoulder numbness.
Triangular Space
Scapular Circumflex ArteryBorders: Superior: Teres minor; Inferior: Teres major; Lateral: Long head of triceps.
Pathology: Key anastomotic branch of subscapular artery forming scapular collateral network around infraspinous fossa.
Triangular Interval
Radial N. + Profunda Brachii A.Borders: Superior: Teres major; Medial: Long head of triceps; Lateral: Shaft of humerus / lateral head of triceps.
Pathology: Conduit into radial (spiral) groove of humerus; vulnerable to midshaft humeral fractures.
Elbow & Wrist Traumatology Matrix
Classical sports and pediatric injuries tested heavily on board vignettes.
Nursemaid's Elbow (Radial Head Subluxation)
Pediatric 1–4 yrsMechanism: Sudden axial traction on an extended, pronated arm (e.g., pulling toddler up by wrist). The annular ligament slips over the head of the radius and becomes trapped in the radiohumeral joint.
Presentation & Reduction: Child holds arm flexed and pronated against body, refusing to move it. Reduction: Flexion with supination (or hyperpronation).
Epicondylitis: Lateral (Tennis) vs. Medial (Golfer's)
Repetitive StrainLateral Epicondylitis (Tennis): Tendinopathy of common extensor origin, specifically Extensor Carpi Radialis Brevis (ECRB); pain on resisted wrist extension and middle finger extension.
Medial Epicondylitis (Golfer's): Tendinopathy of common flexor origin (Pronator Teres & Flexor Carpi Radialis); pain on resisted wrist flexion and pronation.
Scaphoid Fracture & Lunate Dislocation
FOOSH InjuryScaphoid: Anatomic snuffbox tenderness (bounded by EPL medially, EPB/APL laterally). Retrograde blood flow from dorsal scaphoid branch of radial artery → high risk of avascular necrosis and nonunion. Initial radiographs often normal; immobilize and re-image in 10–14 days.
Lunate Dislocation: Anterior displacement compresses the carpal tunnel → acute median nerve compression. Lateral X-ray shows "spilled teacup" sign.
Knee Ligaments, Menisci, Unhappy Triad & Ankle Sprain Topography
Complete anterior vs posterior translation (ACL Lachman vs PCL drawer), C-shaped medial vs O-shaped lateral meniscus, O'Donoghue unhappy triad mechanism, and inversion ankle sprain ligament hierarchy (ATFL "Always Tears First" → CFL → PTFL).

Hip, Knee & Ankle Ligamentous Pathology
| Structure / Injury | Anatomic Mechanism | Clinical Exam Signs | High-Yield Board Concept |
|---|---|---|---|
| Anterior Cruciate Ligament (ACL) | Non-contact pivot/deceleration with knee valgus stress and hyperextension; loud "pop" with rapid hemarthrosis | Lachman test (most sensitive, 30° flexion), Anterior drawer test, Pivot shift test | Originates on lateral femoral condyle, inserts on anterior intercondylar tibia (APEX: Anterior-Posterior, External-Internal). Prevents anterior tibial translation. |
| Posterior Cruciate Ligament (PCL) | Direct posterior blow to proximal tibia on flexed knee ("dashboard injury" in MVA) or severe hyperflexion | Posterior sag test (Godfrey sign), Posterior drawer test | Thicker and stronger than ACL. Originates on medial femoral condyle, inserts on posterior intercondylar tibia. Prevents posterior tibial translation. |
| Medial Collateral Ligament (MCL) | Lateral (valgus) force applied to the knee with foot planted (e.g., clipped on outside of knee in football) | Valgus stress test at 30° knee flexion demonstrates medial joint line laxity and pain | Deep fibers intimately attached to the medial meniscus. Isolated MCL tears managed conservatively; triad involvement requires surgery. |
| Unhappy Triad (O'Donoghue Triad) | Lateral valgus impact on extended or slightly flexed planted foot with twisting rotation | Immediate hemarthrosis, severe instability, positive Lachman, positive valgus stress, joint line tenderness | Classical triad: ACL + MCL + Medial Meniscus. Modern MRI literature shows lateral meniscus is torn more acutely, but board exams still test medial meniscus! |
| Meniscal Tears (Medial vs. Lateral) | Rotational/twisting force on a weight-bearing knee. Degenerative tears occur with minimal trauma in elderly | Joint-line tenderness, mechanical locking/catching, McMurray test (external rotation = medial; internal = lateral) | Outer 1/3 (red zone) has vascular supply and heals; inner 2/3 (white zone) is avascular and requires partial meniscectomy. Medial meniscus is C-shaped and less mobile. |
| Anterior Talofibular Ligament (ATFL) | Inversion injury of plantarflexed foot (e.g., stepping off curb or landing on opponent's shoe) | Anterior drawer test of ankle demonstrates anterior talar translation; swelling/ecchymosis over lateral malleolus | Most commonly injured ligament in ankle sprains ("Always Tears First Ligament"). Severe sprains also tear Calcaneofibular Ligament (CFL). Eversion sprains injure Deltoid Ligament. |
| Achilles Tendon Rupture | Sudden forceful plantarflexion (push-off) or unexpected dorsiflexion; fluoroquinolone (ciprofloxacin) use, elderly runners | Palpable gap in posterior heel, Thompson (Simmonds) test (squeezing calf fails to produce passive plantarflexion) | Formed by gastrocnemius and soleus tendons inserting onto calcaneus. Plantarflexion is severely weakened, but deep flexors (FHL, FDL, TP) allow weak toe flexion. |
| Femoral Neck Fracture vs. Posterior Hip Dislocation | Neck Fracture: Low-energy fall in osteoporotic elderly. Posterior Dislocation: High-speed head-on MVA dashboard impact | Neck Fracture: Shortened, EXTERNALLY rotated leg. Posterior Dislocation: FLEXED, ADDUCTED, INTERNALLY rotated leg | Neck fracture disrupts medial circumflex femoral artery → avascular necrosis of femoral head. Posterior hip dislocation compresses sciatic nerve. |
Fascial Architecture, Compartments & Retinacular Biomechanics
Superficial Fascia
Composition: Loose areolar connective tissue and variable adipose tissue directly underlying the dermis. Contains cutaneous nerves, superficial veins (great/small saphenous, cephalic/basilic), and superficial lymphatic channels.
Investing Deep Fascia
Composition: Dense, organized connective tissue devoid of fat that surrounds individual muscles and neurovascular bundles. In the neck, forms the investing layer of deep cervical fascia enveloping trapezius and sternocleidomastoid.
Intermuscular Septa
Composition: Thick fascial sheets projecting inward from the deep investing fascia to anchor securely onto the periosteum of limb bones (e.g., humerus, femur, tibia/fibula).
Retinacula
Composition: Marked transverse thickenings of deep fascia spanning bony prominences at joints (flexor/extensor retinacula of the wrist and ankle, peroneal retinacula).
Deep Cervical Fascia Layers, Spaces & Mediastinitis Pathways
Investing Layer
Encloses the entire neck like a collar. Splits to envelop the trapezius and sternocleidomastoid (SCM) muscles, as well as the submandibular and parotid salivary glands. Attaches to the mandible, hyoid, clavicle, and manubrium.
Pretracheal Layer
Consists of a muscular part (enclosing infrahyoid strap muscles) and a visceral part (enveloping the thyroid gland, trachea, and esophagus). Continuous posteriorly with the buccopharyngeal fascia covering the pharyngeal constrictor muscles.
Carotid Sheath
Tubular condensation of deep fascia extending from base of skull to root of neck. Contents: Common/Internal Carotid Artery (medial), Internal Jugular Vein (lateral), and Vagus Nerve (CN X) (posterior groove). Ansa cervicalis lies embedded on anterior surface.
Prevertebral Layer
Cylindrical sheath enclosing cervical vertebral column, prevertebral muscles (longus colli/capitis), and scalenes. Surrounds cervical sympathetic trunk and phrenic nerve. Extends laterally as the axillary sheath around the brachial plexus and subclavian artery.
Lies between the buccopharyngeal fascia (anteriorly) and the alar fascia (posteriorly). Extends from the base of the skull inferiorly only to the superior mediastinum (T1–T2), where the alar fascia fuses with the visceral fascia.
Lies between the alar fascia (anteriorly) and the prevertebral fascia (posteriorly). Because there is no inferior anatomic barrier, this potential space extends from the base of the skull straight down through the entire posterior mediastinum to the level of the diaphragm (T12)!
Clinical Vignette Pattern: A child or young adult with an odontogenic abscess, peritonsillar abscess (quinsy), or retropharyngeal cellulitis develops high fever, neck stiffness, dysphagia, and sudden severe pleuritic chest pain with dyspnea. CT scan demonstrates air and fluid tracking down into the posterior mediastinum (→ acute necrotizing mediastinitis, requiring emergent surgical drainage).
Joint Classification Master Matrix (Fibrous, Cartilaginous & Synovial)
| Class & Subtype | Structural Material | Mobility Degree | Anatomical Examples | High-Yield Clinical & Board Correlation |
|---|---|---|---|---|
| Fibrous: Sutures | Dense collagenous sutural ligament | Synarthrosis (Immobile) | Coronal, sagittal, lambdoid sutures of calvaria | Premature closure produces craniosynostosis (scaphocephaly, oxycephaly). Later ossify into synostoses in adulthood. |
| Fibrous: Syndesmosis | Interosseous membrane or ligamentous cord | Amphiarthrosis (Slight) | Middle radioulnar, middle tibiofibular, inferior tibiofibular joint | Disruption of inferior tibiofibular syndesmosis = "High ankle sprain" (external rotation mechanism; Squeeze test positive). |
| Fibrous: Gomphosis | Periodontal ligament (Sharpey fibers) | Synarthrosis (Immobile) | Dentoalveolar syndesmosis (tooth root in bony socket) | Scurvy (Vitamin C deficiency) impairs prolyl/lysyl hydroxylase → defective collagen → periodontal breakdown and loose teeth. |
| Cartilaginous: Primary (Synchondrosis) | Hyaline cartilage | Synarthrosis (Immobile) | Epiphyseal growth plates, spheno-occipital synchondrosis, 1st costochondral joint | Temporary developmental joints that allow bone growth, subsequently undergoing synostosis (fusion). Salter-Harris fractures involve the epiphyseal plate. |
| Cartilaginous: Secondary (Symphysis) | Fibrocartilage disc overlying thin hyaline cartilage plates | Amphiarthrosis (Slight movement) | Pubic symphysis, intervertebral discs, manubriosternal joint | All symphyses reside in the anatomical midline. Designed for high strength and shock absorption. Relaxin softens pubic symphysis during late pregnancy. |
| Synovial: Plane (Gliding) | Articular capsule, synovial fluid, hyaline surfaces | Diarthrosis (Gliding) | Acromioclavicular (AC), intercarpal, zygapophyseal (facet) joints | AC joint separation from direct blow to tip of shoulder (piano key sign). Facet joint tropism causes mechanical axial back pain. |
| Synovial: Hinge (Ginglymus) | Uniaxial cylinder in trough with collateral ligaments | Diarthrosis (Uniaxial Flex/Ext) | Humeroulnar (elbow), talocrural (ankle), interphalangeal (DIP/PIP) | Strong collateral ligaments prevent sideways motion. DIP Heberden nodes and PIP Bouchard nodes in osteoarthritis. |
| Synovial: Pivot (Trochoid) | Central bony pivot enclosed in osteofibrous ring | Diarthrosis (Uniaxial Rotation) | Median atlantoaxial joint (C1–C2 dens), proximal & distal radioulnar joints | C1–C2 allows "no" head rotation. Annular ligament subluxation = Nursemaid's elbow (radial head slips out of pivot ring). |
| Synovial: Condyloid (Ellipsoid) | Oval convex condyle fitting into elliptical concavity | Diarthrosis (Biaxial) | Metacarpophalangeal (MCP 2–5), radiocarpal joint (wrist), atlanto-occipital (C0–C1) | Permits flexion/extension and abduction/adduction (and circumduction), but NO axial rotation. Atlanto-occipital allows "yes" head nodding. |
| Synovial: Saddle (Sellar) | Opposing reciprocal concavo-convex articular surfaces | Diarthrosis (Biaxial + Circumduction) | 1st Carpometacarpal joint (trapeziometacarpal of thumb), sternoclavicular (SC) joint | Provides thumb with unique capability for opposition (grasping and fine motor precision). Common site of basal thumb osteoarthritis. |
| Synovial: Ball-and-Socket (Spheroid) | Spherical head in cup-like socket | Diarthrosis (Multiaxial / 3 DOF) | Glenohumeral joint (shoulder), acetabulofemoral joint (hip) | Highest mobility at expense of stability. Glenohumeral socket is shallow (dependent on rotator cuff/labrum); hip socket is deep (acetabular labrum). |
Temporomandibular Joint (TMJ) Compartmental Biomechanics & Dislocation
Articular Disc & Dual-Compartment Architecture
Biconcave FibrocartilageThe TMJ is a modified hinge / bilateral synovial joint between the mandibular condyle (head) and the mandibular fossa/articular tubercle of the temporal bone. A dense fibrocartilaginous articular disc divides the synovial cavity into two separate functional spaces:
Muscles of Mastication: Functional Vectors
Anterior TMJ Dislocation Mechanism & Manual Reduction
Lockjaw Emergent ReductionPathophysiology: During excessive yawning or forceful dental extraction, the mandibular condyle translates anteriorly over the articular eminence and slips into the infratemporal fossa. Once displaced, powerful spasm of the masseter, temporalis, and medial pterygoid muscles locks the mandible anterior to the articular tubercle, preventing spontaneous closure.
Clinical Triad: Inability to close the mouth (open lock), mandibular prominence, and preauricular depression (empty glenoid fossa palpated anterior to tragus).
Reduction Technique: Place gloved thumbs on the inferior mandibular molars with fingers wrapped externally under the chin. Apply steady DOWNWARD pressure (to overcome masseter/pterygoid spasm and clear the articular eminence) followed by POSTERIOR translation into the mandibular fossa.
Cranial Nerves (I–XII), Skull Base Foramina & Reflex Arcs
Master nucleus origins, skull base exit foramina, functional components, brainstem Rule of 4s, and classic neurologic reflex loops.
Cranial Nerves I–XII Master Compendium
| Nerve | Skull Base Exit | Brainstem Nuclei / Function | Motor & Autonomic Innervation | Sensory & Special Sensation | Clinical Deficit & Board Pearl |
|---|---|---|---|---|---|
| CN I: Olfactory | Cribriform plate (Ethmoid) | Telencephalon / Olfactory bulb; Special Visceral Afferent (SVA) | None | Olfaction (smell) from olfactory neuroepithelium | Anosmia from cribriform plate fracture (head trauma with CSF rhinorrhea). Associated with Kallmann syndrome (hypogonadotropic hypogonadism + anosmia). |
| CN II: Optic | Optic canal (Lesser wing sphenoid) | Diencephalon / Retinal ganglion cells → LGN; Special Somatic Afferent (SSA) | None (Afferent limb of pupillary light reflex) | Vision from retina | Optic neuritis (MS), papilledema, bitemporal hemianopia at chiasm (pituitary tumor). Covered by oligodendrocytes & meninges (vulnerable in MS; elevated ICP transmits along sheath). |
| CN III: Oculomotor | Superior orbital fissure (Sphenoid) | Midbrain (at superior colliculus level); GSE, GVE (parasympathetic) | SR, IR, MR, IO; Levator palpebrae superioris; Pupillary sphincter & ciliary muscle (Edinger-Westphal → ciliary ganglion) | None | Compression (PCom aneurysm / uncal herniation): Blown, dilated pupil FIRST (outer parasympathetic fibers compressed). Microvascular Ischemia (Diabetic): "Pupil-sparing" motor palsy (down-and-out eye, ptosis) because central core fibers are ischemic while outer parasympathetics have pial collateral flow! |
| CN IV: Trochlear | Superior orbital fissure (Sphenoid) | Midbrain (inferior colliculus level); GSE. Only CN that exits DORSALLY and DECUSSATES! | Superior Oblique muscle (depresses eye in adduction, intorts) | None | Vertical diplopia, worse walking down stairs or reading. Patient tilts head AWAY from affected side to compensate for lost intorsion. |
| CN V: Trigeminal (V1, V2, V3) | V1: Sup. Orbital Fissure V2: Foramen Rotundum V3: Foramen Ovale |
Pons (chief sensory, spinal trigeminal, mesencephalic, motor nucleus); GSA, SVE | V3 only: Muscles of mastication (masseter, temporalis, medial/lateral pterygoid), mylohyoid, anterior digastric, tensor tympani, tensor veli palatini | V1: Forehead, cornea (corneal reflex afferent). V2: Mid-face, maxillary teeth. V3: Lower face, mandibular teeth, anterior 2/3 tongue somatic sensation | Trigeminal neuralgia (shooting shock-like pain triggered by touch/chewing; treat with carbamazepine). On jaw opening, mandible deviates TOWARDS side of lesion (unopposed pterygoid). Absent corneal reflex afferent. |
| CN VI: Abducens | Superior orbital fissure (Sphenoid) | Pons (facial colliculus floor of 4th ventricle); GSE | Lateral Rectus muscle (abducts eye) | None | Medial strabismus & horizontal diplopia on looking toward affected side. Longest intracranial subarachnoid course; highly sensitive to elevated ICP ("false localizing sign"). Floats free within cavernous sinus (injured earliest in cavernous sinus thrombosis). |
| CN VII: Facial | Internal acoustic meatus → Stylomastoid foramen | Pons (facial nucleus, superior salivatory, solitary tract); SVE, GVE, SVA, GSA | Muscles of facial expression, stapedius (dampens sound), stylohyoid, posterior digastric. Parasympathetics: Submandibular, sublingual, and lacrimal glands | Taste to anterior 2/3 of tongue (chorda tympani); sensation to external auditory meatus & pinna | UMN (Stroke): Contralateral lower face paralysis with forehead SPARING (bilateral upper face cortical input). LMN (Bell Palsy): Complete ipsilateral paralysis INCLUDING FOREHEAD, hyperacusis (paralyzed stapedius), dry eyes/mouth, lost anterior taste. Corneal reflex efferent limb. |
| CN VIII: Vestibulocochlear | Internal acoustic meatus (Temporal) | Pontomedullary junction; SSA | None | Hearing (cochlear nerve / organ of Corti); Balance & acceleration (vestibular nerve / semicircular canals & otoliths) | Sensorineural hearing loss, vertigo, nystagmus, tinnitus. Vestibular schwannoma (Acoustic Neuroma) at cerebellopontine angle compresses CN VIII, VII, and V; bilateral in Neurofibromatosis type 2 (NF2). |
| CN IX: Glossopharyngeal | Jugular foramen (Temporal/Occipital) | Medulla (nucleus ambiguus, inferior salivatory, solitary tract); SVE, GVE, GVA, GSA, SVA | Stylopharyngeus (elevates pharynx during swallowing). Parasympathetic: Parotid gland (lesser petrosal → otic ganglion → auriculotemporal) | Taste & general sensation to posterior 1/3 of tongue; oropharynx, middle ear cavity; Carotid body & sinus chemo/baroreceptors (Hering nerve) | Loss of gag reflex afferent limb. Glossopharyngeal neuralgia (excruciating lancinating pain in throat/tonsillar bed on swallowing). Carotid sinus hypersensitivity syncope. |
| CN X: Vagus | Jugular foramen (Temporal/Occipital) | Medulla (nucleus ambiguus, dorsal motor nucleus, solitary tract); SVE, GVE, GVA, GSA, SVA | Pharyngeal constrictors, intrinsic laryngeal muscles, levator veli palatini. Parasympathetics to heart, lungs, and GI tract down to splenic flexure | Taste from epiglottis; sensation from larynx, external acoustic meatus (Arnold nerve); aortic arch baroreceptors/chemoreceptors | Uvula deviates AWAY (contralateral) from lesion; hoarseness (recurrent laryngeal nerve injury during thyroidectomy or PDA ligation); dysphagia, lost gag efferent limb. Arnold reflex: ear canal cleaning triggers cough via vagal branch. |
| CN XI: Spinal Accessory | Jugular foramen (Ascends through Foramen Magnum, exits Jugular) | Cervical spinal cord (C1–C5/C6 anterior horns); GSE | Sternocleidomastoid (SCM) and Trapezius muscles | None (purely motor) | Weakness turning head to CONTRALATERAL side (SCM turns head away). Ipsilateral shoulder drooping, impaired shoulder shrugging, and inability to abduct arm above horizontal. Most injured nerve during posterior neck triangle lymph node biopsy! |
| CN XII: Hypoglossal | Hypoglossal canal (Occipital bone) | Medulla (hypoglossal nucleus near midline floor of 4th ventricle); GSE | All intrinsic and extrinsic muscles of tongue EXCEPT Palatoglossus (innervated by CN X!) | None (purely motor) | LMN lesion: Tongue protrudes and deviates TOWARDS the side of the lesion ("lick your wounds") with ipsilateral fasciculations and muscle atrophy. UMN lesion: Tongue deviates contralateral. Injured during carotid endarterectomy. |
Complete Skull Base Foramina & Transmitted Neurovascular Structures
| Cranial Fossa / Bone | Skull Base Foramen | Transmitted Cranial Nerves | Transmitted Vessels & Other Structures | High-Yield Clinical Scenario |
|---|---|---|---|---|
| Anterior Fossa (Ethmoid) | Cribriform Plate | CN I (Olfactory nerve bundles) | Anterior ethmoidal artery | Anterior skull base trauma causes cribriform fracture → anosmia and CSF rhinorrhea (halo sign on filter paper; beta-2 transferrin confirms CSF). |
| Middle Fossa (Sphenoid) | Optic Canal | CN II (Optic nerve) | Ophthalmic artery, central retinal vein | Optic nerve meningioma, ophthalmic artery aneurysm; monocular vision loss. |
| Middle Fossa (Sphenoid) | Superior Orbital Fissure | CN III, IV, V1 (lacrimal, frontal, nasociliary), VI | Superior ophthalmic vein, sympathetic fibers | Superior Orbital Fissure Syndrome: Complete ophthalmoplegia (CN III, IV, VI) + forehead sensory loss (V1) + proptosis. Spares optic canal vision! |
| Middle Fossa (Sphenoid) | Foramen Rotundum | CN V2 (Maxillary nerve) | Emissary veins | Leads into pterygopalatine fossa; middle third facial trauma causes cheek and upper teeth numbness. |
| Middle Fossa (Sphenoid) | Foramen Ovale | CN V3 (Mandibular nerve), Lesser petrosal nerve | Accessory meningeal artery, emissary veins | Mnemonic OVALE: Otic ganglion (just below), V3, Accessory meningeal, Lesser petrosal, Emissary veins. |
| Middle Fossa (Sphenoid) | Foramen Spinosum | Meningeal branch of CN V3 (nervus spinosus) | Middle meningeal artery and vein | Pterion fracture tears middle meningeal artery → rapid arterial expansion of Epidural Hematoma. |
| Middle Fossa (Temporal) | Carotid Canal | Internal carotid sympathetic nerve plexus | Internal Carotid Artery (ICA) | Carotid artery dissection causes Horner syndrome (compression of periarterial sympathetic plexus) + pulsatile tinnitus. |
| Posterior Fossa (Temporal) | Internal Acoustic Meatus | CN VII (Facial), CN VIII (Vestibulocochlear) | Labyrinthine artery (internal auditory a.) | Vestibular Schwannoma (Acoustic Neuroma): Compresses IAM → sensorineural hearing loss, tinnitus, vertigo → late ipsilateral facial droop (CN VII). Bilateral in NF-2! |
| Posterior Fossa (Temporal/Occipital) | Jugular Foramen | CN IX (Glossopharyngeal), CN X (Vagus), CN XI (Accessory) | Internal Jugular Vein, Inferior petrosal sinus, Posterior meningeal artery | Jugular Foramen (Vernet) Syndrome: Glomus jugulare tumor causes loss of gag reflex (IX/X), dysphagia, hoarseness, uvula deviation away, and trapezius/SCM weakness (XI). |
| Posterior Fossa (Occipital) | Hypoglossal Canal | CN XII (Hypoglossal nerve) | Meningeal branch of ascending pharyngeal artery | Lesion causes tongue protrusion deviating TOWARD side of lesion ("licks the lesion"). |
| Posterior Fossa (Occipital) | Foramen Magnum | Spinal roots of CN XI (ascend from C1–C5 to enter skull) | Medulla oblongata, Vertebral arteries, Anterior & posterior spinal arteries, Dural veins | Tonsillar herniation (Chiari I/II or mass effect) compresses medulla → respiratory arrest and death. |
Palate & Face Fusions, Tongue Innervation & Surgical Airway Triangles
Failure of Maxillary & Medial Nasal Prominence Fusion
Failure of the Maxillary Prominence to fuse with the Medial Nasal Prominence (Intermaxillary Segment). Can be unilateral (75%) or bilateral. Results in notch or gap in upper lip and primary palate anterior to incisive foramen.
Failure of Lateral Palatine Shelves Fusion
Failure of the Lateral Palatine Processes (Palatine Shelves) to elevate, swing horizontally, and fuse in the midline with each other, with the nasal septum, and with the primary palate posterior to the incisive foramen.
Tongue Anatomical & Embryological Tripartite Innervation Matrix
- General Sensation: CN V3 (Lingual nerve) — touch, pain, temperature.
- Special Sensation (Taste): CN VII (Chorda tympani) — hitchhikes on lingual nerve.
- General Sensation: CN IX (Glossopharyngeal) — primary sensory limb for gag reflex.
- Special Sensation (Taste): CN IX (Glossopharyngeal) — vallate & foliate papillae.
- Root / Epiglottis: CN X (Superior laryngeal nerve) for taste and touch.
- Motor Supply: CN XII (Hypoglossal) for all muscles EXCEPT Palatoglossus (CN X pharyngeal plexus!)
Retropharyngeal "Danger Space" & Mediastinitis
The Retropharyngeal Space lies between buccopharyngeal fascia and alar fascia. Immediately posterior is the "Danger Space" (between alar and prevertebral fascia), which extends freely from the skull base directly into the posterior mediastinum down to the diaphragm!
Emergency Cricothyrotomy vs. Elective Tracheostomy
Emergency Cricothyrotomy: Performed through the Cricothyroid Membrane (between thyroid cartilage superiorly and cricoid cartilage inferiorly). Quickest emergency surgical airway; enters an avascular, superficial plane below vocal cords; avoids thyroid gland.
Elective Tracheostomy: Performed between tracheal rings 2–3 or 3–4 below the cricoid cartilage. Requires retraction or division of the thyroid isthmus. High risk of torrential hemorrhage from inferior thyroid veins or anomalous Thyroid Ima Artery (~10% prevalence!).
Skull Base Foramina & Neurovascular Transmissions
Complete sphenoid foramina (Superior orbital fissure, Rotundum, Ovale "Standing Room Only"), Middle meningeal artery through Foramen Spinosum (epidural hematoma at pterion), Jugular foramen (CN IX, X, XI, Vernet syndrome), and Hypoglossal canal.

Cavernous Sinus Coronal Anatomy & Orbital Syndromes
Complete coronal cross-section around sella turcica, distinguishing free-floating internal lumen structures (ICA and CN VI) from fibrous lateral wall cranial nerves (CN III, IV, V1, V2), with danger triangle septic thrombosis mechanisms.

High-Yield Cranial Nerve Reflex Arcs
Clinical neurologic reflexes testing afferent/efferent loop integrity.
Corneal Reflex
Touching cornea triggers bilateral eye blink
Efferent: CN VII (Orbicularis oculi)
Pupillary Light Reflex
Light in one eye triggers bilateral pupillary constriction
Efferent: CN III (Bilateral Edinger-Westphal)
Gag Reflex
Touching posterior pharyngeal wall triggers pharyngeal elevation
Efferent: CN X (Nucleus ambiguus)
Jaw Jerk Reflex
Downward tap on chin triggers masseter contraction
Efferent: CN V3 (Motor masseter)
Carotid Sinus Baroreflex
Carotid sinus stretch triggers bradycardia & vasodilation
Efferent: CN X (Dorsal motor nucleus & SA node)
Vestibulo-Ocular Reflex (Doll's Eyes)
Head rotation triggers compensatory conjugate eye movement opposite
Efferent: CN III, IV, VI (via MLF)
Brainstem Rule of 4s & Vertebrobasilar Stroke Localization
Complete anatomical localization matrix: 4 Midline "M" structures (Motor corticospinal, Medial lemniscus, MLF, Motor CN nuclei 3, 4, 6, 12), 4 Lateral "S" structures (Spinothalamic, Spinocerebellar, Sympathetics/Horner, Sensory CN V), PICA/Wallenberg vs AICA syndromes.

External Carotid Hierarchy & The 4 Parasympathetic Ganglia
External Carotid Artery: 8 Named Branches Hierarchy
Accompanies external branch of superior laryngeal nerve; branches into superior laryngeal a. piercing thyrohyoid membrane with internal laryngeal n.
Smallest named branch; ascends vertically along pharyngeal wall to skull base, supplying pharynx, tonsils, and middle ear cavity.
Arises at level of hyoid bone; passes deep to hyoglossus muscle to supply intrinsic and extrinsic tongue muscles and floor of mouth.
Hooks around inferior border of mandible anterior to masseter (palpable pulse); ascends tortuously across face. Tonsillar branch supplies palatine tonsil.
Courses deep to posterior belly of digastric and SCM; grooves the occipital bone to supply posterior scalp.
Ascends posterior to external acoustic meatus to supply auricle, mastoid air cells, and scalp behind ear.
Larger terminal branch. Enters infratemporal fossa → gives off Middle Meningeal Artery (passes through foramen spinosum; pterion trauma → epidural hematoma).
Smaller terminal branch. Ascends anterior to ear with auriculotemporal nerve to vertex of skull. Biopsy site for Giant Cell (Temporal) Arteritis.
The 4 Cranial Parasympathetic Ganglia & Pathway Circuits
| Ganglion | Cranial Nerve Origin | Preganglionic Pathway | Hitchhiking Nerve | Target Viscera & Physiological Action |
|---|---|---|---|---|
| Ciliary Ganglion | CN III (Oculomotor) | Edinger-Westphal nucleus → inferior division of CN III → nerve to inferior oblique | Short ciliary nerves (CN V1) | Sphincter pupillae (miosis) and ciliary muscle (lens accommodation for near vision). |
| Pterygopalatine Ganglion | CN VII (Facial) | Superior salivatory nucleus → Greater petrosal nerve → Nerve of pterygoid canal (Vidian nerve) | Zygomatic (V2) → Lacrimal (V1) | Lacrimal gland (crying/tearing), mucosal glands of nasal cavity, paranasal sinuses, and palate. |
| Submandibular Ganglion | CN VII (Facial) | Superior salivatory nucleus → Chorda tympani → exits petrotympanic fissure | Lingual nerve (CN V3) | Submandibular and Sublingual salivary glands (serous and mucous salivation). |
| Otic Ganglion | CN IX (Glossopharyngeal) | Inferior salivatory nucleus → Tympanic nerve (Jacobson) → Tympanic plexus → Lesser petrosal nerve (foramen ovale) | Auriculotemporal nerve (CN V3) | Parotid salivary gland (profuse watery saliva secretion). |
The Brainstem "Rule of 4s" (Peter Gates)
A foolproof clinical algorithm to localize any brainstem stroke within 30 seconds.
4 Midline Structures Starting with "M"
- Motor pathway (Corticospinal tract): Contralateral arm and leg weakness.
- Medial Lemniscus: Contralateral loss of vibration and proprioception.
- Medial Longitudinal Fasciculus (MLF): Internuclear ophthalmoplegia (INO).
- Motor Cranial Nerve Nuclei: Divisors of 12 that divide equally: CN III, IV, VI, XII (except 1 and 2).
4 Lateral Structures Starting with "S"
- Spinothalamic tract: Contralateral loss of pain and temperature in body.
- Spinocerebellar tract & Peduncles: Ipsilateral limb ataxia.
- Sympathetic descending tract: Ipsilateral Horner syndrome (ptosis, miosis, anhidrosis).
- Sensory Cranial Nerve Nuclei: Do NOT divide into 12: CN V, VII, IX, X.
4 Cranial Nerves per Brainstem Level
- 4 Above Pons: CN I (telencephalon), CN II (diencephalon), CN III, CN IV (midbrain).
- 4 In Pons: CN V, CN VI, CN VII, CN VIII.
- 4 In Medulla: CN IX, CN X, CN XI, CN XII.
Brainstem Stroke Syndromes, Visual Field Defects & Pupillary Circuits
Vascular territories of the brainstem, visual pathway field defects, internuclear ophthalmoplegia, Horner sympathetic cascade, and intracranial hemorrhage types.
Brainstem Stroke Syndromes Master Matrix
| Syndrome | Artery Occluded | Brainstem Level | Ipsilateral Findings | Contralateral Findings | Pathognomonic Distinguishing Feature |
|---|---|---|---|---|---|
| Lateral Medullary (Wallenberg Syndrome) | PICA (or Vertebral artery) | Dorsolateral Medulla |
Dysphagia & hoarseness (Nucleus ambiguus: CN IX, X), lost gag reflex; Ipsilateral Horner syndrome (descending sympathetics); Ipsilateral facial pain/temp loss (Spinal trigeminal nucleus); Ataxia, dysmetria (Inferior cerebellar peduncle); Vertigo, nystagmus, vomiting (Vestibular nuclei) |
Loss of pain & temperature over trunk and extremities (Spinothalamic tract) | Nucleus ambiguus involvement (dysphagia + hoarseness + hiccups) with completely INTACT motor strength! ("Don't pick a PICA" = hoarseness/dysphagia). |
| Lateral Pontine Syndrome | AICA (Anterior Inferior Cerebellar) | Dorsolateral Pons |
Paralysis of face / LMN facial droop (CN VII nucleus); Sensorineural deafness & vertigo (CN VIII nucleus / Labyrinthine a.); Ipsilateral Horner syndrome; Ipsilateral facial sensory loss (CN V); Ataxia (Middle cerebellar peduncle) |
Loss of pain & temperature over body (Spinothalamic tract) | Facial paralysis + Deafness. Mnemonic: "Facial droop = AICA's pooped!" Distinguishes from Wallenberg (where CN VII is spared). |
| Medial Medullary Syndrome | Anterior Spinal Artery (ASA) | Paramedian Medulla | Ipsilateral flaccid tongue paralysis (CN XII hypoglossal nucleus; tongue deviates toward side of lesion on protrusion) |
Contralateral spastic hemiparesis (Corticospinal tract in pyramid); Contralateral loss of vibration & proprioception (Medial lemniscus) |
"Tongue licks the lesion" + contralateral hemiparesis. Spares pain and temperature (spinothalamic is lateral). |
| Parinaud Syndrome (Dorsal Midbrain Syndrome) | Pinealoma / Hydrocephalus (compressing tectum) | Dorsal Midbrain (Superior Colliculi & Pretectal Area) |
Paralysis of upward conjugate gaze (superior colliculus compression); Pseudo-Argyll Robertson pupils: Light-near dissociation (loss of light constriction; near accommodation intact); Bilateral eyelid retraction (Collier sign) |
Convergence-retraction nystagmus on attempted upward gaze (rectus muscle co-contraction) | Compressive syndrome from pineal gland germinoma / pinealoma. Spares motor strength! Downward gaze is characteristically preserved. |
| Weber Syndrome (Superior Alternating Hemiplegia) | PCA paramedian branches | Ventral Midbrain | CN III oculomotor palsy (ipsilateral blown pupil, ptosis, "down-and-out" eye) | Contralateral spastic hemiparesis (Cerebral peduncle / Corticospinal & Corticobulbar tracts) | Midbrain lesion combining ipsilateral CN III palsy with contralateral body hemiplegia. Claude syndrome adds ataxia (red nucleus). |
| Locked-In Syndrome | Basilar Artery (bilateral) | Bilateral Ventral Pons | Bilateral quadriplegia, aphonia, horizontal gaze paralysis | Fully awake, conscious, aware (Reticular Activating System and cortex preserved!) | Vertical eye movements & blinking are SPARED (controlled by midbrain tectum above pons). Patient communicates only via blinking. |
Visual Pathway Lesions & Clinical Field Defects (Anopias)

Visual Pathway Deficits (Anopia Matrix)
Deficit topography matching lesions from the retina to the calcarine cortex.
Monocular Anopia & Amaurosis Fugax
Optic Nerve / CRAOComplete blindness in ipsilateral eye. Amaurosis fugax: Transient painless monocular vision loss ("curtain coming down") caused by retinal artery atheroembolism from ipsilateral carotid stenosis.
Bitemporal Hemianopia
Optic ChiasmCompression of crossing nasal retinal fibers (representing temporal visual fields). Causes: Pituitary adenoma (compresses from below), Craniopharyngioma (Rathke pouch remnant, calcified in children, compresses from above), and ACom aneurysm.
Homonymous Quadrantanopias (Pie in Sky vs. Floor)
Meyer vs. Baum LoopsMeyer Loop (Temporal Lobe - MCA inferior): Contralateral Superior Quadrantanopia ("Pie in the sky"). Passes through temporal horn of lateral ventricle.
Baum Loop (Parietal Lobe - MCA superior): Contralateral Inferior Quadrantanopia ("Pie on the floor"). Passes directly through parietal lobe.
Homonymous Hemianopia with Macular Sparing
PCA InfarctionInfarction of primary visual (calcarine) cortex supplied by Posterior Cerebral Artery (PCA). The macula (central vision) is SPARED because the occipital pole has dual collateral blood supply from the Middle Cerebral Artery (MCA)!
Gaze Pathways & Autonomic Circuits
MLF interneuron communication, Marcus Gunn RAPD, and sympathetic oculomotor wiring.
Internuclear Ophthalmoplegia (INO)
MLF LesionLesion of Medial Longitudinal Fasciculus (MLF): Conjugate horizontal gaze conjugate pair disconnect. On attempted lateral gaze, the ipsilateral eye FAILS TO ADDUCT, and the contralateral abducting eye develops horizontal nystagmus.
Convergence is INTACT (bypasses MLF via pretectal region!). Bilateral INO in a young adult is pathognomonic for Multiple Sclerosis (MS); unilateral INO in elderly is ischemic stroke.
Horner Syndrome 3-Neuron Pathway
Sympathetic InterruptionTriad: Ptosis (Müller superior tarsal muscle), Miosis (paralysis of pupillary dilator), and Anhidrosis (impaired facial sweat glands). Does NOT dilate in darkness!
Circuit: 1st Order: Hypothalamus to C8–T2 ciliospinal center of Budge (hypothalamic/brainstem stroke). 2nd Order: Sympathetic chain over lung apex (Pancoast tumor). 3rd Order: Superior cervical ganglion along internal carotid (carotid dissection / cavernous sinus).
Marcus Gunn Pupil (RAPD)
Afferent Pupillary DefectDiagnosed with "Swinging Flashlight Test". When light is swung from normal eye to affected eye, both pupils paradoxically DILATE (because the affected optic nerve transmits less light sensation than the normal eye). Classical feature of Optic Neuritis in Multiple Sclerosis.
Intracranial Hemorrhages Master Comparison
Biconvex (Lenticular) CT
Anatomy: Fracture of pterion (thin junction of frontal, parietal, temporal, sphenoid bones). Ruptures middle meningeal artery (branch of maxillary a.).
CT Image: Hyperdense biconvex lens that does NOT cross suture lines (dura firmly adherent at sutures).
Crescent-Shaped CT
Anatomy: Rupture of fragile bridging cortical veins crossing subdural space to superior sagittal sinus. Seen in elderly (brain atrophy stretches veins) and chronic alcoholics, shaken baby.
CT Image: Crescent-shaped hematoma that CROSSES suture lines (limited only by dural reflections: falx/tentorium).
Blood in Basal Cisterns
Anatomy: Rupture of saccular (berry) aneurysm at bifurcations in Circle of Willis (most commonly Anterior Communicating Artery). Associated with ADPKD, Marfan, Ehlers-Danlos.
CT Image: Hyperattenuating blood pooling in sulci, sylvian fissures, and basal cisterns.
Basal Ganglia Hyperdensity
Anatomy: Chronic systemic hypertension causes lipohyalinosis → Charcot-Bouchard microaneurysms of lenticulostriate branches of MCA. Most common in putamen of basal ganglia.
CT Image: Focal hyperdense hematoma within brain parenchyma with surrounding edema and mass effect.
Circle of Willis Berry Aneurysms & Ventricular CSF Pathway
Circle of Willis Saccular (Berry) Aneurysms & Neurologic Deficits
Compression: Compresses the Optic Chiasm → Bitemporal Hemianopsia.
Ischemia / Rupture: Ruptures into subarachnoid space (thunderclap headache); anterior cerebral artery ischemia causes contralateral leg paresis and abulia / executive dysfunction.
Compression: Compresses adjacent CN III (Oculomotor nerve).
Hallmark: Ipsilateral blown pupil (mydriasis) with ptosis and "down-and-out" eye. Parasympathetic pupillomotor fibers run superficial on CN III and are compressed first!
Bifurcation: Most commonly located at the first major bifurcation of the MCA in the sylvian fissure.
Deficits: Rupture causes contralateral face and upper extremity weakness, sensory loss, and aphasia (dominant left hemisphere) or hemineglect (right hemisphere).
Ventricular CSF Circulation Route & Hydrocephalus Subtypes
Physical blockage inside ventricular system. Aqueductal stenosis causes enlargement of lateral and 3rd ventricles with normal 4th ventricle. Colloid cyst blocks foramen of Monro.
Impaired resorption by arachnoid villi (scarring from bacterial meningitis or subarachnoid hemorrhage) → symmetric enlargement of all four ventricles.
Triad of "Wet, Wacky, Wobbly": Magnetic gait ataxia (wobbly), urinary incontinence (wet), dementia (wacky). Normal LP opening pressure; gait improves after lumbar puncture tap test!
Embryology, Branchial Apparatus, Organogenesis & Teratogens
Master germ layer derivatives, pharyngeal arches/pouches, cardiovascular septation, gut rotation anomalies, and high-yield pharmacologic teratogenicity.
Weeks 1–4 Developmental Milestones & Gastrulation
Cleavage → Blastocyst Implantation
Fertilization in ampulla of fallopian tube → Zygote.
Rapid mitotic divisions form a 16-cell compact ball: Morula (day 3–4). Fluid enters to form the Blastocyst (day 5) containing:
- Inner Cell Mass (Embryoblast): Gives rise to the embryo proper.
- Trophoblast (Outer Mass): Gives rise to fetal placenta.
Bilaminar Embryonic Disc
Embryoblast splits into 2 germ layers:
- Epiblast: Dorsal columnar layer; gives rise to all 3 definitive embryonic germ layers!
- Hypoblast: Ventral cuboidal layer; forms primary yolk sac lining.
Trophoblast splits into 2 functional layers:
- Cytotrophoblast: Cellular inner layer (mononuclear, mitotic stem cells).
- Syncytiotrophoblast: Outer multinucleated invasive syncytium; invades spiral arteries; secretes β-hCG.
Gastrulation & Trilaminar Disc
Gastrulation: Primitive streak forms in epiblast at caudal end. Epiblast cells invaginate:
- 1st wave displaces hypoblast → Endoderm.
- 2nd wave migrates between layers → Mesoderm.
- Remaining dorsal epiblast → Ectoderm.
Notochord: Epiblast migrating through primitive node forms cellular notochord cord.
Neurulation & 3D Body Folding
Neurulation: Neural plate elevates and fuses into Neural Tube.
- Cranial Neuropore: Closes Day 25 (failure → Anencephaly).
- Caudal Neuropore: Closes Day 27–28 (failure → Spina Bifida / myelomeningocele; elevated MSAFP & AChE).
Embryonic Folding: Cephalocaudal and lateral folding transforms flat 2D disc into 3D cylindrical tube.
Primary Germ Layer Derivatives Master Compendium
Surface Ectoderm & Neuroectoderm
Surface Ectoderm: Epidermis, hair, nails, lens and cornea of eye, inner ear, enamel of teeth, anterior pituitary (Rathke pouch), anal canal below pectinate line, parotid gland.
Neuroectoderm (Neural Tube): Central Nervous System (brain, spinal cord), posterior pituitary (neurohypophysis), retina, optic nerve, pineal gland, astrocytes, oligodendrocytes, ependymal cells.
Neural Crest Cell Migration
Multipotent migratory cells forming diverse peripheral tissues. Memorize via "MOTEL PASS":
- M: Melanocytes
- O: Odontoblasts (dentin)
- T: Tracheal & thyroid cartilages
- E: Enterochromaffin-like cells (Auerbach/Meissner)
- L: Laryngeal cartilages
- P: Parafollicular C cells (calcitonin)
- A: Adrenal medulla (chromaffin cells)
- S: Schwann cells & Spiral septum (heart)
- S: Sympathetic chain & Sensory dorsal root ganglia
Paraxial, Intermediate & Lateral Plate
Paraxial Mesoderm (Somites):
• Sclerotome: Vertebrae, ribs, and axial skeleton.
• Myotome: Skeletal muscles of trunk and limbs.
• Dermatome: Dermis of dorsal back.
Intermediate Mesoderm: Kidneys, ureters, gonads (testes/ovaries), genital ducts (Wolffian/SEED), and adrenal cortex.
Lateral Plate Mesoderm:
• Somatic (Parietal): Parietal peritoneum, pleura, pericardium, limb skeleton.
• Splanchnic (Visceral): Visceral serosa, heart, blood vessels, GI tract wall smooth muscle/connective tissue.
Immune & Spleen: Spleen (mesodermal, celiac blood supply!), microglia (monocyte/macrophage origin).
Epithelial Linings & Glands
GI Epithelial Lining: Gut lumen from pharynx down to pectinate line of anal canal, liver, gallbladder, pancreas (islets & acini).
Respiratory Epithelium: Trachea, bronchi, alveoli (Type I and Type II pneumocytes).
Endocrine & Lymphoid: Thyroid follicular cells, parathyroid glands, thymus.
Urinary Epithelium: Epithelial lining of urinary bladder and female urethra, lower 2/3 of vagina.
Twinning Dynamics, Fetal Shunt Remnants & Amniotic Fluid Homeostasis
Monozygotic Twinning Cleavage Timeline & Placental Architecture
2 separate placentas (or fused) and 2 separate amniotic sacs. Thick 4-layer dividing membrane (amnion-chorion-chorion-amnion). Lowest complication risk.
1 shared placenta, 2 separate amniotic sacs. Thin 2-layer membrane ("T-sign"). ~75% of monozygotic twins. High risk of Twin-Twin Transfusion Syndrome (TTTS) due to unbalanced AV placental shunts!
1 single placenta, 1 single shared amniotic sac with NO dividing membrane. High risk of cord entanglement, knotting, and fetal demise (>50% without intensive monitoring).
Incomplete cleavage of the embryonic disc after gastrulation has commenced. Classified by site of attachment (thoracopagus, craniopagus, omphalopagus).
Fetal Vascular Shunts & Adult Anatomical Remnants
| Fetal Structure | Fetal Function & Oxygenation | Adult Anatomical Remnant | High-Yield Board Malformation / Scenario |
|---|---|---|---|
| Umbilical Vein (1) | Carries oxygenated blood (SaO2 ~80%) from placenta to liver/IVC | Ligamentum Teres Hepatis (Round Ligament) | Courses within falciform ligament; recanalizes in portal hypertension → Cruveilhier-Baumgarten murmur, caput medusae. |
| Ductus Venosus | Shunts ~50% of oxygenated umbilical blood past hepatic sinusoids directly into IVC | Ligamentum Venosum | Fissure for ligamentum venosum separates left lobe from caudate lobe on visceral liver surface. |
| Foramen Ovale | Shunts oxygenated blood from Right Atrium directly into Left Atrium (bypassing lungs) | Fossa Ovalis | Patent Foramen Ovale (PFO): Failure of septum primum & secundum fusion. Permits paradoxical embolism (lower extremity DVT crosses to systemic arterial circulation → cryptogenic stroke!). |
| Ductus Arteriosus | Shunts high-resistance pulmonary artery blood into descending aorta | Ligamentum Arteriosum | Patent Ductus Arteriosus (PDA): Continuous "machine-like" murmur; differential cyanosis. Kept open by PGE2; closed by Indomethacin / NSAIDs. |
| Umbilical Arteries (2) | Carry deoxygenated blood from fetal internal iliac arteries back to placenta | Medial Umbilical Ligaments | Form medial umbilical peritoneal folds on anterior abdominal wall; proximal parts remain open as superior vesical arteries. |
| Urachus (Allantois) | Connects dome of fetal urinary bladder to allantois/umbilicus | Median Umbilical Ligament |
Patent Urachus: Urine leaking from umbilicus. Urachal Cyst: Midline fluid collection; predisposes to urachal adenocarcinoma at dome of bladder! Urachal Sinus: Blind-ended pouch at umbilicus. |
| Vitelline Duct (Omphalomesenteric) | Connects yolk sac to primitive midgut lumen | Obliterated / Disappears | Meckel Diverticulum: Persistent vitelline duct remnant on antimesenteric border of ileum. Rule of 2s: 2% population, 2 inches, 2 feet from ileocecal valve, 2 ectopic tissues (gastric → ulceration/painless bleeding, pancreatic). Diagnosed with Tc-99m pertechnetate scan. |
Mechanisms & Potter Sequence
Causes: Bilateral renal agenesis, Posterior Urethral Valves (males), ARPKD, placental insufficiency, maternal ACE inhibitors / ARBs.
- Pulmonary Hypoplasia: Primary cause of neonatal death!
- Facial Dysmorphism (Potter Facies): Low-set ears, retrognathia, flattened nose.
- Limb Deformities: Clubbed feet (talipes equinovarus).
Mechanisms & Maternal-Fetal Sequelae
Causes: Failure of fetal swallowing or high fetal urine output:
- Impaired Swallowing: Anencephaly (absent neural control), Esophageal Atresia with TEF, Duodenal Atresia (Down syndrome).
- High Output: Maternal Gestational Diabetes (fetal hyperglycemia → osmotic diuresis), Twin-Twin Transfusion (recipient twin), Fetal anemia / Hydrops fetalis.
Pharyngeal (Branchial) Arches, Pouches & Clefts
| Apparatus Unit | Cranial Nerve | Skeletal & Cartilage Structures | Muscular Derivatives | Endodermal Pouches / Ectodermal Clefts |
|---|---|---|---|---|
| 1st Pharyngeal Arch | CN V3 (Mandibular) | Maxilla, Mandible, Malleus, Incus, Sphenomandibular ligament, Meckel cartilage | Muscles of mastication (temporalis, masseter, medial/lateral pterygoids), Mylohyoid, Anterior digastric, Tensor tympani, Tensor veli palatini | Pouch 1: Middle ear cavity, Eustachian tube, Mastoid air cells. Cleft 1: External auditory meatus. |
| 2nd Pharyngeal Arch | CN VII (Facial) | Stapes, Styloid process, Lesser horn of hyoid, Stylohyoid ligament (Reichert cartilage) | Muscles of facial expression, Stapedius, Stylohyoid, Posterior belly of digastric | Pouch 2: Epithelial lining of palatine tonsillar crypts. Cleft 2–4: Cervical sinus (obliterated; persistent = branchial cleft cyst). |
| 3rd Pharyngeal Arch | CN IX (Glossopharyngeal) | Greater horn and body of hyoid bone | Stylopharyngeus muscle (elevates pharynx during swallowing) | Pouch 3: Inferior parathyroid glands & Thymus. (Defective in DiGeorge syndrome 22q11 deletion!). |
| 4th & 6th Pharyngeal Arches | CN X (4th: Superior laryngeal; 6th: Recurrent laryngeal) | Laryngeal cartilages: Thyroid, Cricoid, Arytenoid, Corniculate, Cuneiform | 4th: Pharyngeal constrictors, Cricothyroid, Levator veli palatini. 6th: All intrinsic muscles of larynx (except cricothyroid). |
Pouch 4: Superior parathyroid glands & Ultimobranchial bodies (Parafollicular C cells of thyroid). |
Pharyngeal Pouch Mnemonic: "Ear, Tonsil, Bottom-to-Top"
- 1st Pouch: Ear → Middle ear cavity, Eustachian tube, tympanic membrane interior.
- 2nd Pouch: Tonsil → Palatine tonsil epithelial lining & crypts.
- 3rd Pouch: Bottom → Inferior parathyroid glands + Thymus (descends into mediastinum).
- 4th Pouch: Top → Superior parathyroid glands + Parafollicular C cells.
Branchial Cleft Cyst vs. Thyroglossal Duct Cyst
Branchial Cleft Cyst (Lateral Neck): Failure of 2nd–4th pharyngeal clefts to obliterate → painless fluid-filled mass along the anterior border of the SCM. Does NOT move with swallowing or tongue protrusion!
Thyroglossal Duct Cyst (Midline): Persistent thyroglossal duct tract from foramen cecum. Classic midline anterior neck mass that MOVES UPWARD with swallowing and tongue protrusion.
Pharyngeal Apparatus Architecture (Arches, Pouches & Clefts)
Complete branchial arch nerves (V3, VII, IX, X), muscular and skeletal derivatives (malleus/incus, stapes, stylopharyngeus, cricothyroid vs recurrent laryngeal), pouch derivatives (tympanic cavity, palatine tonsils, inferior parathyroids + thymus, superior parathyroids), and DiGeorge vs Treacher Collins syndromes.

Aortic Arch Derivatives & RLN Asymmetry
Complete 1st–6th aortic arch fates (1st: maxillary; 2nd: stapedial; 3rd: common carotid; 4th: left aorta / right subclavian; 6th: pulmonary & ductus arteriosus) and the embryologic basis of left vs right recurrent laryngeal nerve looping.

Cardiovascular Embryology
Bulbus Cordis → Smooth outflow tracts (aortic vestibule & conus arteriosus).
Sinus Venosus: Left horn → Coronary sinus; Right horn → Smooth right atrium (sinus venarum).
GI Rotation & Atresias
Omphalocele: Midline, covered by peritoneum (trisomy 13/18).
Gastroschisis: Lateral right full-thickness defect, uncovered bowel.
Jejunal/Ileal: Mesenteric vascular accident / ischemic necrosis, "apple-peel" appearance.
Hirschsprung: Neural crest failure → aganglionic colon, delayed meconium >48h.
Renal Organogenesis
Metanephric Mesenchyme (Blastema): Glomeruli, Bowman capsule, PCT, Henle loop, DCT. Reciprocal induction required!
Cardiovascular Embryology & Conotruncal Defects
Complete heart tube segment fates (truncus arteriosus, bulbus cordis, primitive ventricle/atrium, sinus venosus horns) and neural crest conotruncal septation defects: Tetralogy of Fallot (PROVe), Transposition of Great Arteries (TGA), and Persistent Truncus Arteriosus.

Midgut 270° Rotation & Abdominal Wall Closure
Complete timeline: Week 6 herniation, 270° counterclockwise rotation around SMA, Week 10 return; Malrotation with Ladd bands and midgut volvulus; Omphalocele (midline, peritoneal sac) vs Gastroschisis (lateral right, exposed bowel); and Meckel diverticulum (vitelline duct persistence).

Urogenital Duct Differentiation & Renal Migration
Complete internal duct fate under SRY/AMH/Testosterone (Wolffian SEED vs Müllerian tubes/uterus/upper vagina), reciprocal induction between Ureteric Bud and Metanephric Blastema, Horseshoe Kidney entrapment under IMA at L3, and Bicornuate vs Septate uterus.

Teratogen Susceptibility & Toxic Syndromes
Complete timeline of vulnerability (Weeks 1–2 all-or-none vs Weeks 3–8 organogenesis structural malformations) and hallmark drug syndromes: ACE-I (Potter sequence), Isotretinoin (neural crest), Thalidomide (phocomelia), Valproate (NTDs), Lithium (Ebstein anomaly), Warfarin (stippled epiphyses), and DES.

Renal Systems, Duct Regression & External Genitalia Homologies
1. Pronephros
Cervical segment nephrotomes. Completely non-functional in humans; regresses and degenerates completely by week 4.
2. Mesonephros
Interim excretory kidney in 1st trimester. Tubules and duct persist in males to form parts of the male genital ductal system.
3. Metanephros (Permanent)
Formed by reciprocal inductive signaling:
• Ureteric Bud: Ureter, renal pelvis, calyces, collecting ducts.
• Metanephric Blastema: Glomeruli, Bowman capsule, PCT, Henle loop, DCT.
Genetic Sex Determination & Internal Duct Differentiation
SRY gene on Y chromosome encodes Testis-Determining Factor (TDF) → primitive sex cords become testes:
- Sertoli Cells: Secrete Anti-Müllerian Hormone (AMH / MIF) → regression of Paramesonephric (Müllerian) ducts.
- Leydig Cells: Secrete Testosterone → stimulates Mesonephric (Wolffian) ducts to develop into "SEED" (Seminal vesicles, Epididymis, Ejaculatory duct, Ductus deferens).
Default pathway in absence of SRY, AMH, and Testosterone:
- Wolffian Ducts: Degenerate automatically without testosterone stimulation.
- Müllerian Ducts: Persist and fuse in midline → Fallopian tubes, Uterus, Cervix, and Upper 1/3 of Vagina.
- Müllerian Fusion Anomalies: Septate uterus (failed resorption of central septum; recurrent miscarriages), Bicornuate uterus (incomplete fundal fusion).
External Genitalia Homologies & Congenital Malformations
| Embryonic Structure | Male Homologue (driven by DHT) | Female Homologue (Estrogen / Default) | Clinical Pathology & Board Pearl |
|---|---|---|---|
| Genital Tubercle | Glans penis, Corpus cavernosum & spongiosum | Glans clitoridis, Corpus cavernosum clitoridis, Bulbs of vestibule | Epispadias: Abnormal dorsal urethral opening on top of penis from faulty tubercle positioning; strongly associated with bladder exstrophy. |
| Urogenital (Urethral) Folds | Ventral shaft of penis (spongy urethra) | Labia minora | Hypospadias: Failure of urethral folds to fuse on ventral aspect of penis → ventral urethral opening. Do NOT circumcise (prepuce needed for repair!). |
| Urogenital Sinus | Prostate gland, Bulbourethral (Cowper) glands | Greater vestibular (Bartholin) glands, Skene glands, Lower 2/3 of vagina | Dual vaginal origin: Upper 1/3 from paramesonephric ducts (mesoderm); lower 2/3 from urogenital sinus (endoderm). Imperforate hymen = persistent membrane at junction. |
| Labioscrotal Swellings | Scrotum | Labia majora | Virilization of labioscrotal swellings occurs in 46,XX Congenital Adrenal Hyperplasia (21-hydroxylase deficiency → androgen excess → ambiguous genitalia). |
High-Yield Board Teratogen Matrix
| Teratogenic Agent | Target Organ System | Specific Congenital Malformation Pattern | Board Exam Scenario & Mechanism |
|---|---|---|---|
| ACE inhibitors / ARBs | Renal & Craniofacial | Renal dysgenesis, oligohydramnios sequence, hypocalvaria (skull bone hypoplasia) | Angiotensin II essential for fetal renal development; blockade causes fetal anuria and pulmonary hypoplasia. |
| Isotretinoin (Retinoids) | Craniofacial, Cardiac & CNS | Microtia (external ear absence), thymic aplasia, cleft palate, hydrocephalus, conotruncal heart defects | Disrupts Hox gene expression and neural crest cell migration. Strict iPLEDGE program: 2 negative pregnancy tests + 2 birth control methods. |
| Lithium | Cardiovascular | Ebstein Anomaly: Apical displacement of tricuspid leaflets → severe tricuspid regurgitation, "atrialization" of right ventricle | Used for bipolar disorder; maternal lithium exposure causes massive right atrial enlargement and cyanosis in neonate. |
| Valproate & Carbamazepine | Central Nervous System | Neural tube defects (Myelomeningocele / Spina bifida), fingernail hypoplasia, developmental delay | Inhibits folate absorption; maternal supplementation requires 4 mg/day of folic acid in women taking antiepileptic drugs. |
| Phenytoin | Fetal Hydantoin Syndrome | Microcephaly, dysmorphic craniofacial features, cleft lip/palate, hypoplastic nails & distal phalanges, cardiac defects | Anticonvulsant causing oxidative stress and folate disruption during organogenesis. |
| Warfarin | Skeletal & CNS | Nasal bone hypoplasia, stippled epiphyses (chondrodysplasia punctata), optic atrophy, microcephaly | Inhibits vitamin K gamma-carboxylation of osteocalcin. Heparin does NOT cross the placenta and is anticoagulant of choice in pregnancy! |
| Thalidomide | Musculoskeletal | Phocomelia (flipper limbs), amelia, micromelia of long bones | Historically prescribed for morning sickness; binds cereblon to degrade angiogenic transcription factors in limb buds. |
| Tetracyclines (Doxycycline) | Teeth & Bones | Permanent tooth discoloration (yellow-brown staining), enamel hypoplasia, inhibition of long bone growth | Chelates divalent calcium ions in developing teeth and bones; contraindicated in pregnancy and children <8 years. |
| Aminoglycosides (Gentamicin) | Auditory / Vestibular | Congenital sensorineural deafness and vestibular toxicity (CN VIII damage) | Accumulates in endolymph and destroys hair cells of the cochlea. |
| Fetal Alcohol Syndrome (FAS) | Neurodevelopmental & Facies | Smooth philtrum, thin upper vermilion border, short palpebral fissures, microcephaly, intellectual disability, VSD/ASD | Most common preventable cause of intellectual disability in the United States. Impairs cell migration and neuronal apoptosis. |
Thoracoabdominal Cavities, Portocaval Shunts & Pelvic Anatomy
Mediastinal compartments, diaphragm apertures, portocaval anastomoses, groin hernias, retroperitoneal boundaries, and pudendal pelvic nerve blocks.
Diaphragm Apertures & Hiatal Hernias
"I 8 10 Eggs At 12"T8: Caval Opening (Vena Cava Hiatus)
Central TendonContents: Inferior Vena Cava (IVC) and terminal branches of the Right Phrenic Nerve. Pierces the central tendon (dilates during inspiration to facilitate venous return!).
T10: Esophageal Hiatus
Right CrusContents: Esophagus, Anterior and Posterior Vagal Trunks, esophageal branches of left gastric vessels. Formed by muscular fibers of the right crus of diaphragm.
Hiatal Hernias: Sliding (Type 1, 95%): Gastroesophageal junction slides upward into posterior mediastinum; causes GERD. Paraesophageal (Type 2): GE junction stays in normal position, but gastric fundus herniates beside esophagus; high risk of strangulation!
T12: Aortic Hiatus
Median Arcuate LigamentContents: Abdominal Aorta, Thoracic Duct, and Azygos Vein. Passes behind the median arcuate ligament; does not pierce diaphragmatic muscle (blood flow unaffected by breathing!).
Congenital Diaphragmatic Hernias
Bochdalek vs. MorgagniBochdalek Hernia (85–90%): Posterolateral pleuroperitoneal membrane defect; Bochdalek = Back and Left. Abdominal viscera compress fetal lung → severe pulmonary hypoplasia (cause of death). Morgagni Hernia: Rare anteromedial retrosternal defect.
Mediastinal Compartments & Masses
The 4 "T"sAnterior Mediastinum (The 4 "T"s)
Thymoma • Thyroid • Teratoma • Terrible LymphomaBounded anteriorly by sternum, posteriorly by pericardium and great vessels. Classic anterior mediastinal masses:
- Thymoma: Strongly associated with Myasthenia Gravis (anti-AChR antibodies) and Pure Red Cell Aplasia.
- Thyroid: Substernal ectopic thyroid or multinodular goiter plunging into thoracic inlet.
- Teratoma / Germ Cell: Mature teratoma, seminoma, choriocarcinoma, endodermal sinus tumor.
- Terrible Lymphoma: Hodgkin lymphoma (nodular sclerosis subtype in young females) with Reed-Sternberg cells.
Middle Mediastinum
Heart & CystsContains pericardium, heart, ascending aorta, pulmonary trunk, phrenic nerves, tracheobronchial lymph nodes. Masses: Bronchogenic cysts, pericardial cysts, lymphoma, aortic arch aneurysms.
Posterior Mediastinum
Neurogenic TumorsContains thoracic aorta, esophagus, thoracic duct, azygos/hemiazygos veins, vagus nerves, sympathetic trunk. Masses: Neurogenic tumors (Schwannoma, neurofibroma, neuroblastoma in pediatrics), esophageal tumors.
Diaphragmatic Apertures, Inguinal Canal & Retroperitoneal Traps
Complete diaphragm levels (T8 IVC, T10 Esophagus/Vagus, T12 Aorta/Thoracic duct/Azygos "I 8 10 Eggs At 12"), Inguinal canal & Hesselbach triangle (Direct medial vs Indirect lateral to inferior epigastrics), Femoral hernia canal, and Left Renal Vein nutcracker compression under SMA.

Pulmonary Hilum (RALS), Dependent Aspiration & Triangle of Koch Conduction
Pulmonary Hilum: "RALS" Rule
Relationship of the Pulmonary Artery to the Mainstem Bronchus at the lung hilum:
- Right pulmonary artery is Anterior to right bronchus (RA).
- Left pulmonary artery is Superior to left bronchus (LS).
Dependent Bronchopulmonary Segments
Aspiration pneumonia and lung abscess localize according to patient posture at the time of aspiration:
- Supine Position (e.g. Alcoholic / Seizure / Coma): Aspirate flows into the Superior (Apical) segment of the Right Lower Lobe (RLL) or the Posterior segment of the Right Upper Lobe (RUL).
- Upright / Standing Position: Aspirate gravitates into the Posterior Basal segment of the Right Lower Lobe (RLL).
Cardiac Nodes, Triangle of Koch Boundaries & Coronary Dominance
Located subepicardially in the crista terminalis at the junction of the SVC and Right Atrium.
Arterial supply: SA Nodal Artery (branch of RCA in ~60%; LCx in ~40%).
Located in the posteroinferior interatrial septum within the Triangle of Koch:
- Tendon of Todaro (superior)
- Septal tricuspid leaflet (inferior)
- Coronary sinus ostium (base)
Supplied by AV nodal artery from PDA.
Dominance determined by origin of Posterior Descending Artery (PDA):
• Right Dominant (85–90%): PDA from RCA.
• Left Dominant (10%): PDA from LCx.
Transverse Thoracic Plane (Sternal Angle of Louis / T4–T5)
The transverse thoracic plane is an imaginary horizontal line passing from the sternal angle of Louis (junction of manubrium and sternal body) anteriorly to the intervertebral disc between T4 and T5 posteriorly. It serves as the primary anatomical boundary dividing the superior mediastinum from the inferior mediastinum (which is further subdivided into anterior, middle, and posterior compartments by the pericardial sac).
Rib 2
Articulates at sternal angle; starting point for counting ribs
Aortic Arch
Ascending aorta ends; arch begins & arches posteriorly to become descending aorta
Tracheal Carina
Trachea bifurcates into right and left mainstem bronchi
Pulmonary Trunk
Bifurcates into right and left pulmonary arteries beneath aortic arch
Left Recurrent Laryngeal
Loops under aortic arch and ligamentum arteriosum to ascend tracheoesophageal groove
Azygos Vein
Arches over root of right lung to empty into the Superior Vena Cava
Nerves
Deep cardiac plexus located on anterior tracheal bifurcation
Thoracic Duct
Crosses from right side to left side behind esophagus at T4–T5
Portocaval (Portosystemic) Anastomoses & Clinical Sequelae
| Clinical Site | Portal Venous System | Systemic (Caval) Venous System | Pathophysiology in Portal Hypertension | Clinical Presentation & Treatment |
|---|---|---|---|---|
| Gastroesophageal Junction | Left Gastric Vein (Coronary) | Azygos Vein → Superior Vena Cava | Retrograde portal flow through left gastric vein dilates submucosal esophageal veins into tortuous collaterals. | Esophageal Varices: Massive, life-threatening upper GI bleeding (hematemesis). Treat with Octreotide, endoscopic band ligation, non-selective beta-blockers (propranolol, nadolol). |
| Umbilicus (Anterior Abdominal Wall) | Paraumbilical Veins (Ligamentum teres) | Superficial & Inferior Epigastric Veins | Recanalization of the umbilical vein in the falciform ligament shuttles portal blood outward into abdominal subcutaneous veins. | Caput Medusae: Radiating engorged periumbilical subcutaneous veins. Blood flows radiating outward away from umbilicus (differentiates from IVC obstruction where flow is entirely cephalad!). |
| Anorectal Junction | Superior Rectal Vein (from IMV) | Middle & Inferior Rectal Veins (Internal Iliac) | Backpressure from inferior mesenteric vein drains laterally and inferiorly into systemic pelvic circulation. | Anorectal Varices: Tortuous submucosal collaterals at pectinate line. Cause painless hematochezia. Note: Internal hemorrhoids are non-cirrhotic venous plexus prolapses, distinct from true varices. |
| TIPS Procedure (Interventional Radiology) | Portal Vein Branch (Right) | Hepatic Vein (Right) → IVC | Transjugular intrahepatic portosystemic shunt creates an artificial channel directly connecting the portal vein to the hepatic vein. | Decompresses Portal HTN: Controls refractory variceal bleeding and ascites. Major Board Complication: Can precipitate or worsen Hepatic Encephalopathy (unmetabolized neurotoxins like ammonia bypass hepatic processing). |
Peritoneal Ligaments, The Pringle Maneuver & Omental Bursa
Hepatoduodenal Ligament
Pringle ManeuverConnects liver to 1st part of duodenum; constitutes free edge of lesser omentum. Contains the Portal Triad:
- Hepatic Artery Proper
- Hepatic Portal Vein
- Common Bile Duct
Epiploic Foramen (Winslow)
Lesser Sac EntryOnly natural communication between greater and lesser peritoneal sacs (omental bursa). Strict surgical boundaries:
- Anterior: Hepatoduodenal ligament (portal triad)
- Posterior: Inferior Vena Cava (IVC)
- Superior: Caudate lobe of liver
- Inferior: 1st part of duodenum
Splenorenal Ligament
Splenectomy HazardConnects spleen to left kidney posterior body wall. Transmits the Splenic Artery and Vein and the Tail of the Pancreas.
Gastrosplenic & Falciform
Vascular CollateralsGastrosplenic: Connects greater curvature to spleen; contains Short Gastric Vessels (vulnerable to gastric infarction in splenic a. embolization due to poor collaterals!).
Falciform Ligament: Connects liver to anterior wall; carries Ligamentum Teres Hepatis (remnant of left umbilical vein → recanalizes in caput medusae).
Inguinal & Femoral Hernias Comparison
Definitive surgical differentiation of groin hernia types based on vascular landmarks.
Direct Inguinal Hernia
Medial to EpigastricsAnatomy: Protrudes through Hesselbach's Triangle (Borders: Rectus abdominis medially, Inferior epigastric vessels laterally, Inguinal ligament inferiorly). Caused by acquired weakness of the transversalis fascia in older men.
Spermatic Coverings: Covered ONLY by external spermatic fascia. Does NOT enter the scrotum; felt on pulp of finger on exam.
Indirect Inguinal Hernia
Lateral to EpigastricsAnatomy: Enters the deep inguinal ring LATERAL to the inferior epigastric vessels. Caused by failure of the processus vaginalis to close (congenital patent canal). Most common hernia overall (male infants and young adults).
Spermatic Coverings: Covered by all 3 layers of spermatic fascia (internal spermatic, cremasteric, external spermatic). Enters scrotum; touches fingertip on invagination.
Femoral Hernia
Inferior to Inguinal LigamentAnatomy: Protrudes through the femoral ring into the femoral canal, INFERIOR to the inguinal ligament and MEDIAL to the femoral vein (NAVEL: Nerve, Artery, Vein, Empty space, Lymphatics).
High-Yield Concept: More common in females due to wider pelvis. Has the highest rate of bowel incarceration and strangulation due to narrow, rigid femoral ring!
Inguinal Canal Precise Boundaries & Spermatic Cord Fascial Hierarchy
- Anterior Wall: External Oblique Aponeurosis (plus internal oblique laterally).
- Posterior Wall: Transversalis Fascia (reinforced medially by Conjoint Tendon).
- Roof (Superior): Arching musculoaponeurotic fibers of Internal Oblique & Transversus Abdominis.
- Floor (Inferior): Inguinal Ligament of Poupart and Lacunar Ligament medially.
- External Spermatic Fascia: Derived from External Oblique Aponeurosis.
- Cremasteric Muscle & Fascia: Derived from Internal Oblique Muscle (L1–L2 genital branch of genitofemoral n.).
- Internal Spermatic Fascia: Derived from Transversalis Fascia.
Abdominal Wall Fascia, Arcuate Line & Specialized Hernias
Superficial Fascial Layers & Extravasation
- Camper's Fascia: Superficial, fatty layer containing subcutaneous fat and cutaneous nerves/vessels. Thickens in obesity.
- Scarpa's Fascia: Deeper, thin, membranous layer with minimal fat. Fuses inferiorly with the fascia lata of the thigh just below the inguinal ligament.
- Perineal Continuations: Scarpa's fascia continues into the perineum as Colles' fascia and into the scrotum/penis as Dartos fascia.
- Clinical Significance: In straddle trauma with anterior urethral rupture (spongiosum), extravasated urine and blood can fill the scrotum, penis, and lower anterior abdominal wall deep to Scarpa's fascia, but cannot spread into the thigh due to Scarpa's attachment to the fascia lata.
Rectus Sheath Shift at Arcuate Line
- Superior to Arcuate Line (Upper 3/4):
• Anterior Sheath: External oblique aponeurosis + anterior leaf of internal oblique aponeurosis.
• Posterior Sheath: Posterior leaf of internal oblique aponeurosis + transversus abdominis aponeurosis + transversalis fascia. - Inferior to Arcuate Line (Lower 1/4):
• All 3 aponeuroses (external oblique, internal oblique, transversus abdominis) transition to pass ANTERIOR to the rectus abdominis muscle.
• Posteriorly: Rectus abdominis rests directly on only the transversalis fascia and parietal peritoneum. - Rectus Sheath Hematoma: Inferior epigastric vessels enter the sheath by crossing over the arcuate line; vulnerable to shear rupture during severe coughing (paroxysms) or anticoagulation. Below the arcuate line, hematomas can cross the midline or dissect into the pelvis!
| Hernia Eponym | Anatomic Location & Defect | Classic Board Presentation & Traps |
|---|---|---|
| Spigelian Hernia | Along the linea semilunaris (lateral edge of rectus abdominis), typically at or near the level of the arcuate line. | Interparietal hernia lying deep to an intact external oblique aponeurosis. Often non-palpable or mistaken for abdominal wall mass; high strangulation rate. |
| Richter's Hernia | Incarceration of only a portion of the antimesenteric circumference of bowel wall within the hernia ring. | Lethal Trap: Bowel lumen remains patent, allowing flatus/stool passage! Can progress to localized strangulation, necrosis, and perforation WITHOUT signs of mechanical obstruction. |
| Obturator Hernia | Protrusion through the obturator canal alongside the obturator nerve and vessels into the medial compartment of the thigh. | Elderly, emaciated, multiparous females. Howship-Romberg sign: Inner thigh pain exacerbated by hip extension, adduction, and internal rotation, relieved by hip flexion. |
| Littre's Hernia | Hernia sac containing a Meckel diverticulum (persistent vitelline duct). | Most commonly found in inguinal (50%), femoral (20%), or umbilical hernias. Prone to painless rectal bleeding or perforation. |
| Pantaloon Hernia | Simultaneous direct AND indirect hernia sacs straddling the inferior epigastric vessels. | Saddlebag hernia presentation; both the deep inguinal ring and Hesselbach's triangle floors are defective. |
Pancreatic Buds, Annular Pancreas & Intestinal Watershed Zones
Ventral vs. Dorsal Bud Fates
Ventral Pancreatic Bud: Arises from hepatic diverticulum; forms the uncinate process, inferior head, and main pancreatic duct (of Wirsung).
Dorsal Pancreatic Bud: Forms superior head, neck, body, tail, and accessory pancreatic duct (of Santorini).
Griffith Point & Sudeck Point
Watershed zones are borderland areas located at the extreme periphery of adjacent arterial supply territories. Highly susceptible to hypoperfusion and nonocclusive ischemic colitis during systemic shock or hypotension:
- Griffith Point (Splenic Flexure): Watershed boundary between the Superior Mesenteric Artery (SMA) (middle colic a.) and Inferior Mesenteric Artery (IMA) (left colic a.).
- Sudeck Point (Rectosigmoid Junction): Watershed boundary between the lowest sigmoidal branch of the IMA and the Superior Rectal Artery (with internal iliac collateral supply).
Pectinate (Dentate) Line Neurovascular & Pathologic Master Matrix
| Anatomic Feature | Above Pectinate Line (Hindgut / Endoderm) | Below Pectinate Line (Proctodeum / Ectoderm) |
|---|---|---|
| Embryologic Origin | Hindgut (Endoderm) | Proctodeum (Surface Ectoderm) |
| Epithelial Lining | Columnar epithelium (glandular mucosa) | Stratified squamous non-keratinized → keratinized skin |
| Arterial Supply | Superior rectal artery (terminal branch of Inferior Mesenteric Artery, IMA) | Inferior rectal artery (branch of internal pudendal artery ← internal iliac artery) |
| Venous Drainage | Superior rectal vein → IMV → Splenic vein → Portal Vein (Portal circulation) | Inferior rectal vein → Internal pudendal vein → Internal iliac vein → IVC (Systemic circulation) |
| Lymphatic Drainage | Internal iliac lymph nodes & Inferior mesenteric nodes | Superficial inguinal lymph nodes (palpable groin adenopathy) |
| Nerve Innervation |
Visceral Autonomic Innervation: Inferior hypogastric plexus. Insensitive to somatic pain, temperature, or touch; sensitive ONLY to stretch/distension. |
Somatic Sensory Innervation: Inferior rectal nerve (branch of Pudendal nerve S2–S4). Exquisitely sensitive to pain, cutting, touch, and temperature! |
| Hemorrhoid Pathology | Internal Hemorrhoids: Dilation of superior rectal venous plexus. Manifest as painless bright red bleeding and mucosal prolapse (can be banded without anesthesia). | External Hemorrhoids: Dilation of inferior rectal venous plexus. Thrombosis causes exquisite, agonizing, sharp somatic pain (covered by somatic skin). |
| Malignancy Type | Adenocarcinoma (colorectal lineage) | Squamous Cell Carcinoma (HPV-associated, HPV 16/18) |
| Anal Fissure Location | N/A | Tear in anoderm distal to pectinate line, classically in posterior midline due to poor vascular perfusion. Extremely painful with bowel movements; leads to sentinel skin tag and hypertrophied anal papilla. |
Pelvic Neuroanatomy & Retroperitoneal Boundaries
Obstetric nerve blocks, autonomic sexual reflexes, and retroperitoneal organ topography.
Pudendal Nerve Block (S2–S4)
Obstetric AnesthesiaLandmark: Palpated transvaginally at the Ischial Spine through the sacrospinous ligament. Pudendal nerve exits greater sciatic foramen, crosses ischial spine, enters lesser sciatic foramen through pudendal (Alcock) canal.
Innervation: Sensation to perineum, vulva, lower vagina, and external anal sphincter; motor to levator ani and external urethral/anal sphincters. Anesthetizes perineum during episiotomy.
Autonomics: "Point and Shoot"
Erection & EjaculationPoint = Parasympathetic (S2–S4 Pelvic Splanchnic Nerves): Nitric oxide → cGMP → cavernous helicine artery relaxation → engorgement & erection. Sildenafil inhibits PDE-5 to preserve cGMP.
Shoot = Sympathetic (T11–L2 Hypogastric Nerves): Alpha-1 adrenergic stimulation contracts vas deferens and seminal vesicles → emission and ejaculation.
Retroperitoneal Organs ("SAD PUCKER")
Peritoneal ReflectionS: Suprarenal (Adrenal) glands | A: Aorta & IVC | D: Duodenum (2nd, 3rd, 4th parts) | P: Pancreas (head, neck, body; tail is in splenorenal ligament!) | U: Ureters | C: Colon (ascending & descending) | K: Kidneys | E: Esophagus (lower thoracic) | R: Rectum (upper 2/3).
Surgical Landmark: "Water under the bridge": Ureter passes UNDER the uterine artery in females and under vas deferens in males!
Thoracic Wall Layer Hierarchy & Intercostal Neurovascular Topography
Complete 9-Layer Cross-Section (Superficial to Deep)
Thoracentesis Landmark Protocol
Safe Needle EntryNeedle Placement Rule: The needle is ALWAYS inserted directly OVER the superior border of the rib below to avoid the primary intercostal neurovascular bundle (VAN) sheltered in the subcostal groove of the rib above.
Tube Thoracostomy: "Safe Triangle"
Chest Tube InsertionIndicated for hemothorax, large pneumothorax, or empyema. Insertion is restricted to the "Safe Triangle" to avoid long thoracic nerve, internal thoracic vessels, and diaphragm injury:
- Anterior Border: Lateral edge of Pectoralis Major muscle.
- Posterior Border: Anterior edge of Latissimus Dorsi muscle.
- Inferior Border: Horizontal line at the 5th intercostal space (nipple line / inframammary crease).
- Apex: Base of axilla.
Internal Thoracic Artery Bifurcation & Caval-Caval Venous Bypasses
Internal Thoracic Artery (ITA / LIMA)
1st Part SubclavianOriginates from the 1st part of the subclavian artery, descends 1–2 cm lateral to the sternum behind the upper 6 costal cartilages.
- Superior Epigastric Artery: Pierces diaphragm between sternal and costal slips, enters rectus sheath behind rectus abdominis.
- Musculophrenic Artery: Traverses along costal margin, supplies diaphragm and 7th–9th intercostal spaces.
Coronary Bypass (CABG): The Left Internal Mammary Artery (LIMA) is the gold-standard conduit for grafting the Left Anterior Descending (LAD) coronary artery due to superior 10-year patency (>90%).
Systemic Arterial Collateral Bypasses
Epigastric ShuntSuperior vs. Inferior Epigastric Anastomosis: Inside the rectus sheath, the Superior Epigastric Artery (from ITA → subclavian) forms an extensive end-to-end anastomosis with the Inferior Epigastric Artery (from External Iliac Artery).
Coarctation of the Aorta: In post-ductal coarctation, high subclavian pressure drives blood through ITA → anterior intercostals and superior epigastric → inferior epigastric → external iliac → lower extremities. Dilated, tortuous intercostal arteries erode inferior rib margins producing notching of ribs 3–8 ("Roesler sign").
Leriche Syndrome (Aortoiliac Occlusion): Blood flows retrograde from ITA → superior epigastric → inferior epigastric → distal iliofemoral beds.
Azygos & Hemiazygos Venous System
Caval-Caval ShuntForms a posterior thoracic venous conduit connecting the Inferior Vena Cava (IVC) and Superior Vena Cava (SVC):
- Azygos Vein: Ascends on the right side of thoracic vertebral bodies, arches over the right lung root at T4 to drain directly into the SVC.
- Hemiazygos Vein: Ascends on left lower thorax (T9–T12), crosses right behind aorta/esophagus at T9 to join azygos.
- Accessory Hemiazygos: Drains left mid-thorax (T5–T8), crosses right at T8.
Diaphragmatic Crura, Arcuate Ligaments & Arterial Supply
Right vs. Left Crural Topography & Arcuate Ligaments
- Median Arcuate Ligament: Fibrous arch bridging the right and left crura anterior to the abdominal aorta at T12. Compression of the celiac axis = Median Arcuate Ligament Syndrome (MALS): postprandial abdominal angina and epigastric bruit.
- Medial Arcuate Ligament: Thickening of fascia over the Psoas Major muscle (anchors to L1/L2 body and transverse process).
- Lateral Arcuate Ligament: Thickening of fascia over the Quadratus Lumborum muscle (anchors to L1 transverse process and 12th rib).
Tri-Source Arterial Supply of the Diaphragm
Because of its complex embryological origin from 4 embryonic precursors, the diaphragm receives blood from three distinct arterial pathways:
Inferior Phrenic Arteries (Direct from Abdominal Aorta)
Pair of vessels arising directly from the anterior surface of the abdominal aorta immediately above the celiac trunk. Supplies the vast majority of the abdominal (inferior) surface of the diaphragm, also giving off the superior suprarenal arteries to adrenal glands.
Pericardiacophrenic & Musculophrenic Arteries
Pericardiacophrenic: Accompanies the phrenic nerve between fibrous pericardium and mediastinal pleura, supplying central diaphragm and pericardium. Musculophrenic: Terminal branch of ITA supplying costal periphery of diaphragm.
Superior Phrenic Arteries
Small paired branches from the lowermost thoracic aorta supplying the posterior superior dome of the diaphragm.
Bronchopulmonary Segment Hierarchy & Contralateral Lymphatic Crossover
Segmental Autonomy & Surgical Segmentectomy
10 Right vs. 8–10 LeftA bronchopulmonary segment is the functional and anatomical sub-unit of the lung, surrounded by connective tissue septa.
Central Structures (Intrasegmental): Each segment has its own dedicated tertiary segmental bronchus and segmental branch of the pulmonary artery running centrally together into the segment apex.
Peripheral Structures (Intersegmental): The pulmonary veins and lymphatic drainage run in the connective tissue septa BETWEEN adjacent segments.
Surgical Cleavage Plane: Because veins run between segments, a thoracic surgeon can resect a diseased bronchopulmonary segment (segmentectomy) without compromising the arterial supply or ventilation of adjacent healthy segments!
Contralateral Lymphatic Drainage Pattern (Board Trap!)
Metastatic CrossoverPulmonary lymph flows from deep intrapulmonary nodes → bronchopulmonary (hilar) nodes → tracheobronchial (carinal) nodes → paratracheal nodes → broncho-mediastinal lymph trunks:
A primary bronchogenic carcinoma in the left lower lobe frequently presents with contralateral right-sided mediastinal lymphadenopathy and right supraclavicular adenopathy.
Spinal Cord Tracts, Cross-Sectional Lesions & Radiculopathy Matrix
Ascending and descending tract cross-sections, classic myelopathy syndromes (Brown-Séquard, Syrinx, SCD, ASA occlusion), and C5–S4 radicular localization.
Spinal Cord Lesion Syndromes Master Matrix
| Syndrome | Anatomic Structures Damaged | Motor Clinical Manifestations | Sensory Clinical Manifestations | High-Yield Board Concept |
|---|---|---|---|---|
| Brown-Séquard Syndrome (Hemisection) | Unilateral hemisection of cord (stab wound, bullet, asymmetric tumor/disc) |
Ipsilateral UMN paralysis below lesion (lateral corticospinal tract). Ipsilateral LMN flaccid paralysis at the exact level of the lesion (anterior horn). |
Ipsilateral loss of vibration & proprioception below lesion (dorsal columns). Contralateral loss of pain & temperature beginning 1–2 dermatomal segments BELOW lesion (spinothalamic). |
Classic exam trap: Spinothalamic tract fibers cross 1–2 segments above entry, so contralateral pain/temp loss starts 2 levels below physical lesion! |
| Syringomyelia (Syrinx) | Fluid-filled cavity expanding within central canal, compressing Anterior White Commissure first | Late extension into anterior horns causes hand muscle atrophy and LMN weakness. |
Bilateral "cape-like" loss of pain & temperature across shoulders and upper arms. Fine touch, vibration, and proprioception are SPARED (dorsal columns preserved!). |
Strongly associated with Chiari I malformation (downward herniation of cerebellar tonsils >5mm through foramen magnum). Patient burns hands without feeling pain. |
| Subacute Combined Degeneration (SCD) | Vitamin B12 (Cobalamin) deficiency, Vitamin E deficiency, or Copper deficiency | Bilateral spastic paresis, hyperreflexia, extensor plantar responses (lateral corticospinal tracts). | Bilateral loss of vibration & proprioception with severe sensory ataxia and positive Romberg sign (dorsal columns). | Defective myelin synthesis due to methylmalonyl-CoA accumulation. Differentiated from folate deficiency by elevated methylmalonic acid (MMA) and neurologic deficits! |
| Anterior Spinal Artery (ASA) Occlusion | Infarction of anterior 2/3 of spinal cord (spares posterior 1/3 supplied by paired posterior spinal arteries) | Sudden bilateral flaccid paraplegia transitioning to spastic paraplegia below lesion level (bilateral corticospinal tracts). |
Bilateral loss of pain and temperature below lesion level (spinothalamic tracts). Vibration & Proprioception are COMPLETELY INTACT! |
Often occurs during thoracic aortic aneurysm repair disrupting the Artery of Adamkiewicz (great anterior radiculomedullary artery, usually T9–T12). |
| Amyotrophic Lateral Sclerosis (ALS) | Progressive degeneration of both Upper Motor Neurons (corticospinal) and Lower Motor Neurons (anterior horns / brainstem) | Asymmetric limb weakness, fasciculations, muscle atrophy (LMN) combined with hyperreflexia, spasticity, and Babinski sign (UMN). | NO sensory deficits! (Sensory pathways, bowel/bladder sphincters, and cognitive function completely spared). | Pathology shows TDP-43 cytoplasmic aggregates; 10% familial with SOD1 (superoxide dismutase) mutation. Treat with Riluzole (glutamate antagonist) or Edaravone. |
| Tabes Dorsalis (Tertiary Syphilis) | Slow progressive demyelination and degeneration of Dorsal Columns and Dorsal Nerve Roots | Motor pathways spared, but severe sensory ataxia causes high-stepping "slapping" gait. | Impaired vibration and joint position sense, sensory ataxia, positive Romberg sign, severe sudden "lightning pains" in legs. | Associated with Argyll Robertson pupils (accommodate but do not react to light: "prostitute's pupil"). Absent deep tendon reflexes (hyporeflexia). |
Spinal Cord Tracts, Cross-Sectional Lesions & Radiculopathy
Complete tract decussations (DCML in caudal medulla, Corticospinal in pyramids, Spinothalamic via anterior white commissure in spinal cord) and classic myelopathies: Brown-Séquard hemisection, Anterior Spinal Artery infarct (dorsal column sparing), Syringomyelia cape-like loss, and posterolateral lumbar disc herniation transiting root impingement.

Cervical & Lumbosacral Radiculopathy Matrix
| Nerve Root | Disc Herniation Level | Key Motor Weakness | Sensory Dermatome Loss | Deep Tendon Reflex Tested |
|---|---|---|---|---|
| C5 | C4–C5 disc (C5 nerve root exits ABOVE C5 vertebra) | Deltoid (shoulder abduction) and Biceps | Lateral upper arm / shoulder (sergeant's badge area) | Biceps Reflex (C5, C6) |
| C6 | C5–C6 disc | Biceps and Wrist Extensors (extensor carpi radialis) | Lateral forearm, thumb, and index finger | Brachioradialis Reflex (C5, C6) |
| C7 | C6–C7 disc (most common cervical radiculopathy!) | Triceps (elbow extension), Wrist flexors, Finger extension | Middle finger (palmar and dorsal) | Triceps Reflex (C7, C8) |
| C8 | C7–T1 disc (C8 exits between C7 and T1) | Finger flexors (grip strength: flexor digitorum profundus) | Medial forearm, ring finger, and little finger (5th digit) | None |
| T1 | T1–T2 disc | Intrinsic hand muscles (interossei: abduction/adduction of fingers) | Medial upper arm | None |
| L4 | L3–L4 disc (paracentral herniation compresses transiting L4 root) | Tibialis Anterior (ankle dorsiflexion and foot inversion), Quadriceps | Medial lower leg, anterior knee, and medial malleolus | Patellar (Knee-Jerk) Reflex (L2, L3, L4) |
| L5 | L4–L5 disc (most common lumbar radiculopathy!) | Extensor Hallucis Longus (great toe dorsiflexion), Gluteus medius | Dorsum of foot, 1st webspace, and lateral calf | None (or medial hamstring) |
| S1 | L5–S1 disc | Gastrocnemius & Soleus (plantarflexion: inability to walk on toes), Gluteus max | Lateral malleolus, lateral foot, and sole (plantar surface) | Achilles (Ankle-Jerk) Reflex (S1, S2) |
| S2–S4 | Massive central disc herniation / tumor (Cauda Equina) | Anal sphincter tone loss, urinary retention / overflow incontinence | Saddle anesthesia (perianal, perineum, buttocks, posterior thigh) | Bulbocavernosus & Anal Wink Reflex (S3, S4) |
High-Yield Clinical Dermatome Landmarks (C2 to S4)
Occiput
Posterior skull and occipital protuberance.
Turtleneck
High turtleneck shirt collar area.
Low Collar
Low collar shirt line; acromioclavicular joint.
Thumb ("Six-Shooter")
Thumb & radial forearm (make gun with hand = 6).
Middle Finger
Middle finger (palmar and dorsal surfaces).
Pinky Finger
Ring and little fingers (4th and 5th digits).
Nipple Line
"Teat-4" = at the horizontal nipple line.
Xiphoid
Inferior margin of sternal xiphoid process.
Umbilicus
"Belly but-ten" = early appendicitis pain.
Inguinal Ligament
"L1 = 1nguinal" groove / pelvic crease.
Kneecaps
"Down on all 4s" = anterior patella & medial malleolus.
Pinky Toe & Heel
Lateral malleolus, small toe, and Achilles reflex.
Developmental Curvatures, Uncovertebral Joints & Scottie Dog Radiography
Primary Kyphoses vs. Secondary Lordoses
Primary Curvatures (Kyphosis, concave anteriorly): Thoracic and Sacral curvatures. Present at birth, reflecting original fetal flexed posture ("C-shape"). Maintained by anterior wedging of thoracic vertebral bodies.
Secondary Curvatures (Lordosis, concave posteriorly):
• Cervical Lordosis: Develops at 3–4 months when infant begins holding head erect.
• Lumbar Lordosis: Develops at 12–18 months when toddler begins upright standing and weight-bearing ambulation.
Uncovertebral Joints of Luschka (C3–C7)
Formed during childhood (around age 7–10) between the uncinate processes projecting superiorly from lateral margins of cervical vertebral bodies and the beveled inferolateral margins of the adjacent vertebra above.
The "Scottie Dog" Anatomic Correlation
Atypical Vertebrae, Craniocervical Ligaments & High-Vulnerability Transition Zones
Atypical Cervical Vertebrae (C1, C2, C7)
Composed of paired lateral masses connected by short anterior and longer posterior arches. Superior articular facets are concave and kidney-shaped, articulating with occipital condyles (atlanto-occipital joint: permits "yes" nodding flexion/extension). Transverse foramen transmits the vertebral artery and venous plexus.
Jefferson (Burst) Fracture: Axial load on vertex of skull (e.g., diving into shallow pool) forces lateral masses outward, rupturing the anterior and posterior arches of C1.
Strongest cervical vertebra. The dens (odontoid process) projects superiorly from the body to serve as the pivot axis around which C1 rotates (atlantoaxial joint: permits "no" shaking rotation).
Characterized by a prominent, long, non-bifid spinous process that is easily palpable at the base of the neck. Universal surface landmark used by clinicians to count vertebral levels.
Clay-Shoveler's Fracture: Avulsion fracture of the C6/C7 or T1 spinous process due to forceful traction of the trapezius and rhomboids during sudden heavy lifting.
High-Vulnerability Spinal Transition Zones
Spinal transition junctions represent abrupt biomechanical boundaries between mobile, lordotic segments and rigid, kyphotic segments, concentrating rotational shear and axial load:
Transition from hypermobile cervical lordosis (coronal oblique facets allowing multidirectional movement) to the rigid, rib-cage-anchored thoracic kyphosis. Prone to missed fracture-dislocations on plain radiographs unless visualized via "Swimmer's view" or CT.
Abrupt Facet Orientation Shift: Thoracic facets lie in the coronal plane (permitting axial rotation while limiting flexion/extension). At T12–L1, facets abruptly shift to the sagittal plane (permitting flexion/extension while blocking rotation).
Clinical Consequence: Over 50% of all spinal compression fractures and Chance fractures (seatbelt hyperflexion-distraction injury) occur at T12–L1 due to stress concentration where a rigid rotatory column meets a mobile sagittal hinge.
The lordotic wedge-shaped L5 vertebral body rests on the downward-sloping sacral promontory, subjecting L5 to enormous continuous anterior gravitational shear stress.
Intervertebral Disc Herniation: Exiting vs. Traversing Root Localization
Cervical Spine: Exit ABOVE Rule
C1–C8 RootsThe Rule: There are 7 cervical vertebrae and 8 cervical spinal nerves. C1 through C7 nerve roots exit ABOVE their correspondingly numbered vertebra (C1 exits above C1, C5 exits above C5, C7 exits above C7). The C8 nerve root exits BELOW C7 (between C7 and T1).
C5–C6 Disc Herniation: Impinges the C6 nerve root → Weakness of biceps and brachioradialis (elbow flexion/pronation), diminished brachioradialis reflex, numbness over the lateral forearm and thumb.
C6–C7 Disc Herniation: Impinges the C7 nerve root → Weakness of triceps (elbow extension) and wrist flexors, diminished triceps reflex, numbness over middle finger.
Lumbar Spine: Exit BELOW & Herniation Vectors
Posterolateral vs Far LateralThe Rule: Thoracic, lumbar, and sacral nerve roots exit BELOW their correspondingly numbered pedicle/vertebra (L4 exits below L4 pedicle through the L4–L5 neural foramen).
Posterolateral Herniation (95% of cases): Impinges the TRAVERSING nerve root (the nerve passing down to exit at the foramen below).
• L4–L5 Posterolateral Herniation: Impinges L5 → Foot drop, weakness of ankle dorsiflexion (tibialis anterior) and great toe extension (EHL), sensory loss over dorsal foot and web space between digits 1 and 2. Reflexes remain normal!
• L5–S1 Posterolateral Herniation: Impinges S1 → Weakness of gastrocnemius/soleus (cannot walk on tiptoes, impaired plantarflexion), diminished or absent Achilles reflex, sensory loss over lateral foot and sole.
Far Lateral / Foraminal Herniation (5% of cases): Protrudes directly into the neural foramen and impinges the EXITING nerve root.
• Far lateral L4–L5 Herniation: Impinges L4 → Quadriceps weakness (difficulty rising from chair), diminished or absent patellar tendon reflex, numbness over medial lower leg and medial malleolus.
Spinal Ligament Architecture & Lumbar Puncture Trajectory
Longitudinal & Segmental Ligaments
- Anterior Longitudinal Ligament (ALL): Broad, thick, fibrous band covering the anterior surfaces of vertebral bodies from occiput to sacrum. Resists hyperextension of the vertebral column. Only spinal ligament torn in severe whiplash hyperextension injuries!
- Posterior Longitudinal Ligament (PLL): Runs along the anterior wall of the vertebral canal (posterior surfaces of vertebral bodies). Resists hyperflexion. Narrower and weaker in the lumbar spine, leaving the posterolateral annulus fibrosus unsupported → primary mechanical reason why >95% of disc herniations occur posterolaterally!
- Ligamentum Flavum: Dense, yellow elastic tissue connecting the laminae of adjacent vertebrae. Preserves upright posture and assists spinal extension. Traversed during epidural anesthesia and LP; provides the tactile 'pop' or sudden loss of resistance.
- Interspinous Ligaments: Connect adjacent spinous processes from root to apex.
- Supraspinous Ligament: Strong fibrous cord connecting the tips of spinous processes from C7 to sacrum; merges cranially into the ligamentum nuchae.
Lumbar Puncture 7-Layer Needle Path (L3–L4 / L4–L5)
To harvest CSF safely without injuring the spinal cord, the needle is introduced at the L3–L4 or L4–L5 interspace (guided by the intercristal / Tuffier's line connecting the iliac crests). The conus medullaris ends at L1–L2 in adults (L3 in infants).
1. Skin
2. Subcutaneous fat / superficial fascia
3. Supraspinous ligament
4. Interspinous ligament
5. Ligamentum flavum ← First tactile "pop" / loss of resistance
6. Epidural space (site of epidural block; contains internal vertebral plexus)
7. Dura mater + Arachnoid mater ← Second subtle "pop" into CSF
8. Subarachnoid space (CSF reservoir; cauda equina nerve roots float away)
*Note: The pia mater is intimately adherent to the neural tissue and is NEVER penetrated in a standard lumbar puncture.
COMLEX DO MSK Biomechanics, Sacral Axes & Viscerosomatics
High-yield functional biomechanics essential for COMLEX Level 1 & 2: rib motion mechanics, sacral torsion diagnostics, fibular head entrapment, and autonomic viscerosomatic reflexes.
Rib Mechanics, Motion Planes & Somatic Dysfunction
Pump-Handle Motion
Primary Axis: Coronal (costovertebral-costosternal line). Motion occurs primarily in the sagittal plane, increasing the anteroposterior (AP) diameter of the chest during inhalation.
Palpation: Evaluated at the mid-clavicular line on the anterior rib cage.
Bucket-Handle Motion
Primary Axis: Sagittal (AP line). Motion occurs primarily in the coronal plane, increasing the transverse diameter of the thoracic cage during inhalation.
Palpation: Evaluated at the mid-axillary line laterally.
Caliper Motion
Primary Axis: Vertical. Floating ribs move outward and posterior during inhalation, and inward and anterior during exhalation.
Palpation: Evaluated posteriorly along the lower rib cage margins.
Key Rib Identification Rules
Inhalation Dysfunction (Stuck UP): Ribs move freely into inhalation but are restricted in exhalation. The KEY RIB is the LOWEST rib in the dysfunctional group (it prevents the ribs above it from descending).
Exhalation Dysfunction (Stuck DOWN): Ribs move freely into exhalation but are restricted in inhalation. The KEY RIB is the HIGHEST rib in the dysfunctional group (it blocks the ribs below it from ascending).
Muscle Energy Target Activation Muscles
- Rib 1: Anterior and Middle Scalenes
- Rib 2: Posterior Scalene
- Ribs 3–5: Pectoralis Minor
- Ribs 6–9: Serratus Anterior
- Ribs 10–11: Latissimus Dorsi
- Rib 12: Quadratus Lumborum
Rib Motion Mechanics (Pump, Bucket, Caliper) & Sacral Torsions
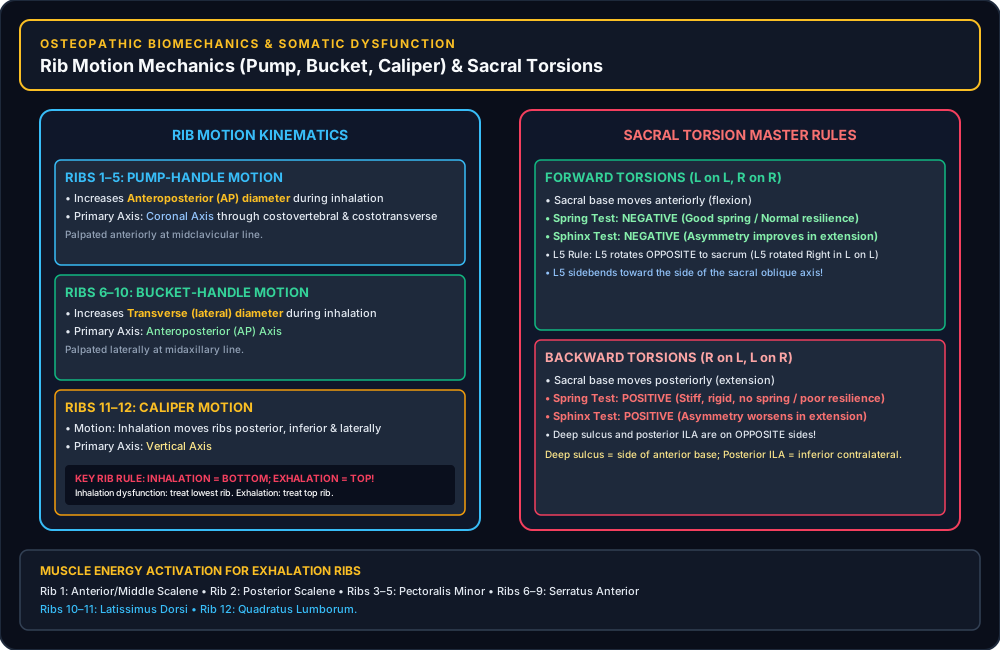
Sacral Axes, Torsions & L5 Relationship
| Sacral Diagnosis | Type | Lumbosacral Spring Test | Sphinx (Hyperextension) Test | L5 Rotation & Sidebending Rules |
|---|---|---|---|---|
| Left-on-Left (L on L) Forward Torsion | Forward (Physiologic) | Negative (Good spring) | Negative (Asymmetry improves in extension) | L5 rotates OPPOSITE to sacral rotation (L5 rotated Right, Sidebent Left). Sacral base anterior on Right. |
| Right-on-Right (R on R) Forward Torsion | Forward (Physiologic) | Negative (Good spring) | Negative (Asymmetry improves in extension) | L5 rotates OPPOSITE to sacral rotation (L5 rotated Left, Sidebent Right). Sacral base anterior on Left. |
| Right-on-Left (R on L) Backward Torsion | Backward (Non-Physiologic) | Positive (Poor / No spring) | Positive (Asymmetry worsens in extension) | L5 rotates in the SAME DIRECTION as sacral rotation (L5 rotated Right, Sidebent Left). Sacral base posterior on Right. |
| Left-on-Right (L on R) Backward Torsion | Backward (Non-Physiologic) | Positive (Poor / No spring) | Positive (Asymmetry worsens in extension) | L5 rotates in the SAME DIRECTION as sacral rotation (L5 rotated Left, Sidebent Right). Sacral base posterior on Left. |
Fibular Head Biomechanics & Peroneal Entrapment
Direct relationship between fibular head somatic dysfunction and common peroneal nerve compression.
Posterior Fibular Head Dysfunction
High Risk for Foot DropMechanics: Proximal fibular head moves posterior; distal fibula (lateral malleolus) moves anterior. The ankle and foot prefer plantarflexion and inversion (supination injury / inverted ankle sprain).
Nerve Vulnerability: The Common Peroneal (Fibular) Nerve wraps around the neck of the fibula; posterior displacement puts traction or compression on the nerve → foot drop, loss of dorsiflexion, and numbness of foot dorsum.
Anterior Fibular Head Dysfunction
Eversion PreferenceMechanics: Proximal fibular head moves anterior; distal lateral malleolus moves posterior. The ankle and foot prefer dorsiflexion and eversion (pronation injury).
Viscerosomatic Autonomic Reflex Map (T1–L2)
Essential sympathetic spinal levels tested on every COMLEX exam.
2K Master Topography & Active Recall Plates (16 Core Systems)
Dual-mode interactive atlas plates. Click any plate to open the full-resolution Prometric Workstation with pan, zoom, board pearls, and challenge drills.
Pharyngeal Apparatus Architecture
Arches, pouches, clefts, DiGeorge 22q11 deletion, Treacher Collins, and branchial cleft cysts.
Aortic Arches & RLN Asymmetry
Arches 1–6 adult arteries, Left RLN aortic arch loop vs Right RLN subclavian loop, and coarctation rib notching.
Cardiovascular Embryology & Septation
Truncus arteriosus, bulbus cordis, sinus venosus, Tetralogy of Fallot (PROVe), TGA, and persistent truncus.
Midgut 270° Rotation & Ventral Wall
Week 6 to Week 10 rotation around SMA, Ladd bands, midgut volvulus, Omphalocele vs Gastroschisis, and Meckel.
Urogenital Ducts & Renal Ascent
SRY/AMH regulation, Wolffian SEED vs Müllerian duct differentiation, Ureteric bud induction, and Horseshoe kidney IMA entrapment.
Teratogen Susceptibility & Syndromes
Organogenesis window (Weeks 3–8), ACE-I/Potter, Isotretinoin, Thalidomide phocomelia, Valproate NTDs, and Lithium Ebstein anomaly.
Brachial Plexus Root-to-Terminal
5 roots, 3 trunks, 3 cords around axillary artery, 5 terminal nerves, Erb palsy (C5-C6), Klumpke claw (C8-T1), and winged scapula.
Hand Neurovascular & Cutaneous Maps
Palmar/dorsal sensory maps, carpal tunnel thenar eminence sensation sparing, recurrent branch (OAF), and ulnar claw vs benediction.
Lower Extremity Nerves & Gait
Femoral, obturator, common fibular (PED / foot drop), tibial (TIP / tarsal tunnel), and superior gluteal Trendelenburg gait.
Rotator Cuff & Scapular Spaces
Supraspinatus 0–15°, infraspinatus/teres minor external rotation, subscapularis on lesser tubercle, and quadrangular space.
Brainstem Rule of 4s & Strokes
4 Midline (M) vs 4 Lateral (S) structures, PICA (Wallenberg / nucleus ambiguus) vs AICA (facial droop) stroke localization.
Skull Base Foramina & Transmissions
Sphenoid foramina (S-R-O), Foramen Spinosum (MMA epidural hematoma at pterion), Jugular foramen (Vernet), and Hypoglossal canal.
Cavernous Sinus Coronal Topography
Coronal relations around sella, ICA & CN VI in lumen, CN III/IV/V1/V2 in wall, septic thrombosis, and carotid-cavernous fistula.
Diaphragmatic Apertures & Groin
T8/T10/T12 apertures, Direct (medial) vs Indirect (lateral) inguinal hernias, femoral hernia ring, and renal nutcracker left varicocele.
Knee & Ankle Ligaments Topography
ACL Lachman vs PCL drawer, medial C-shaped vs lateral O-shaped meniscus, Unhappy triad of O'Donoghue, and ATFL inversion sprains.
Spinal Cord Tracts & Radiculopathy
DCML, Corticospinal, and Spinothalamic decussations, Brown-Séquard, ASA anterior infarction, Syringomyelia, and disc herniation.
Authentic Cross-Sectional Radiology & Surgical Anatomy
High-yield clinical CT, MRI, and 3D MRA scans correlated directly with surgical landmarks and board vignette traps.

Brachial Plexus Cords & Axillary Artery
Landmarks: Lateral, posterior, and medial cords named relative to the second part of the axillary artery deep to pectoralis minor.
Clinical Clue: "M" shape formed on anterior surface of axillary artery by musculocutaneous, median, and ulnar nerves.

Cavernous Sinus Cross-Section
Landmarks: Sits on either side of sella turcica (pituitary). Traversing through sinus lumen: Internal Carotid Artery and CN VI (Abducens).
Lateral Wall Structures (Superior to Inferior): CN III (Oculomotor), CN IV (Trochlear), CN V1 (Ophthalmic), CN V2 (Maxillary). CN V3 does NOT pass through!

Circle of Willis & Saccular Aneurysms
Landmarks: Anastomosis between anterior circulation (internal carotids → ACA, MCA) and posterior circulation (vertebrals → basilar → PCAs) linked by ACom and PCom.
Aneurysm Sites: 1) ACom (most common): Bitemporal hemianopsia (optic chiasm compression). 2) PCom: Ipsilateral CN III palsy with blown, dilated pupil and ptosis.

Renal Nutcracker Compression
Landmarks: Compression of the left renal vein as it traverses horizontally between the Superior Mesenteric Artery (anteriorly) and the Abdominal Aorta (posteriorly).
Clinical Presentation: Left flank pain, hematuria, and left testicular varicocele in males (because left gonadal vein drains into left renal vein at 90° angle!).

Inguinal Canal & Hesselbach's Triangle
Hesselbach's Triangle Borders: 1) Lateral border of rectus abdominis (medially), 2) Inferior epigastric vessels (laterally), 3) Inguinal ligament (inferiorly).
Direct Inguinal Hernia: Protrudes through floor of Hesselbach's triangle MEDIAL to inferior epigastrics. Indirect Hernia: Enters deep ring LATERAL to inferior epigastrics.

Knee Cruciate Ligaments & Menisci
Landmarks: ACL: Passes from lateral femoral condyle to anterior intercondylar tibia. PCL: Stronger, thicker posterior band (dashboard injury; posterior sag test).
Unhappy Triad: Lateral impact on flexed planted knee tears 1) ACL, 2) MCL, and 3) Medial Meniscus.

Celiac Axis & Splenic Vein Relations
Celiac Branches (T12): 1) Left gastric artery, 2) Splenic artery, 3) Common hepatic artery.
Pathophysiology: Chronic pancreatitis can cause Splenic Vein Thrombosis → backpressure into short gastric veins → isolated gastric fundic varices.

Pouch of Douglas & Ureteral Crossing
Landmarks: Pouch of Douglas: Lowest point of peritoneal cavity in standing female, sampled via posterior vaginal culdocentesis.
Surgical Landmark: "Water under the bridge": The ureter passes INFERIOR to the uterine artery in cardinal ligament.
Interactive Nerve Lesion Locator
Filter anatomical trauma sites and nerve entrapments to reveal motor deficits, sensory loss, and clinical physical exam signs.